Friday, September 22, 2006

Agfa Impax 6.x…The Saga Continues

I’m not the only one who has noticed some gaps or glitches in Impax 5.2 and even 6.0. One Agfa user mentions these problems (rewritten for clarity) on APUG (the Agfa user’s group) with reading MRI under 5.2:

1. Triangulation - the localization tool in Impax 5.2 doesn’t work as well as some of the more simply designed tools in eFilm or Amicas. With the latter two, you just click on a point, and all other windows lock on to the same level. With Impax, the corresponding tool does work, but not on images that are linked by position to other windows. Good, but not quite there. As with lots of other tools, you have to click it again (actually twice) to turn it off. The soon-to-be-famous Agfa toggle.

2. Speaking of linked sequences, it is possible to link a bunch of sequences together. We even have a wizard button that will sync all the planes of an MRI together. Unfortunately they all scroll at the same time, and you can’t just click one button and link everything together. Amicas links the planes individually and intuitively, as do others, and with one button.

3. There is no easy way to display location of a slice on every other orthogonal plane, and have it update as you scroll through slices, without a "scout" window, nor is there a way to show the first and last image on other planes. The scout scroll tool in Impax is by contrast extremely cumbersome and finicky. Amicas and others do this with a single button.

4. Measurement tools - dragging across an object, clicking to get a measurement, then moving the number aside to measure the perpendicular dimension (to avoid the numbers overlapping right in the middle of the lesion being measured) is simply too many steps for what should be a much simpler process.

5. Too many functions in 5.2 require several mouse clicks, which is frustrating for many rads who are used to the functionality of tools which require a single mouse click.

6.What passes for a spine-labeling tool and hanging protocols are essentially impossible to use in 5.2.

The list ended with this: “One wonders how much end user (i.e. radiologist) input was sought at the time of development.” Someone else comments, “Perhaps enough voices will together prompt the necessary improvements in functionality. It is apparent that no working radiologists were involved in the development of the initial product.” Now, I was told that there were 12 radiologists on the Agfa advisory panel that approved Impax 6.0, and yes, they had experience with other systems. Still, given that Impax 6.0 does things in very similar fashion to Impax 5.2, I have to wonder a little bit about that. The majority of these difficulties persist into 6.0, which has a viewing component that is very similar under the hood to what we have with 5.2. Keep in mind for CT triangulation and whatnot that the "simple MPR" tool has been removed, but it may be replaced at your option with Voxar 3D.

The good news is that at least some of these things are to be fixed by RSNA 2006, or so we hear. That would be nice.

A friend of mine on the other coast has been having a world of trouble with his 6.x installation and migration from another vendor. “The doctors’ workstations crash all the time, AGFA applies a patch and says this will fix it and in a couple of days the stations are crashing again. The rads say AGFA sucks! Even so, they do all agree that we are in a better place than we were with the old vendor.”

Obviously, Agfa needs to work on a few things.

I am probably a bigger fan of Agfa's than they are of mine. I do believe I got several of their execs rather upset with some of my blog posts on Impax 6.0, but I'll stand by most of what I posted, and I corrected the areas that were inaccurate.

Agfa's big push with Impax 6.0 was the migration to the .NET architecture, a laudable goal. The "front end" to the interface was completely revamped from Impax 4.x-5.x. The new interface is very different overall, for those of you who have not sampled it. There is a great deal of "toggling" between screens of information. I liken it to a control panel on the Enterprise (the starship, that is) where a wave of the hand would load in a different set of options. Having used Impax 6.0 as a web-appendage for call purposes over the last several months, I still find this quite disorienting. I like having a worklist constantly visible on the third (or fourth or fifth) monitor. (As an aside, we are having to add a fifth monitor to our four high-res monitor stations to accommodate the eventual migration to Impax 6.0 from 5.2.)

While the main interface was revamped, the Impax 6.0 viewing component is really a re-skinned port of the viewer from Impax 5.2 with all its good and bad points. The main deficiency I find (beyond the lack of usable tools as others have outlined) is the persistence of the clone-window concept. With other systems (and Amicas I think does this quite well), one can drag any sequence to any viewport or window. I like to view my CT's with multiple window settings, for example. Now this can be done, and I even have a wizard to do it, but it requires spawning a clone window to do so. I want to be able to do this within the main viewer itself. I could go on, but you get the idea.

As I mentioned above, Agfa told us last RSNA that "12 radiologists" were on their panel for approval of Impax 6.0, and they ultimately agreed on the final release. I suggested at the time that these radiologists must have been exclusive Agfa users, because of the stasis of the viewer; I was told that was not the case. Having sat on advisory boards of other vendors, I can attest to the difficulty in getting more than two radiologists to agree on anything, so I can see how things might have gone in the Agfa meetings. Still, now is the time to fix and revamp Impax 6.0, before it gets entrenched as it stands. We can only hope that Agfa can fix some of these problems by RSNA, or I’m going to be “toggled” to death.

Tuesday, September 19, 2006

Visitor Twenty Thousand!!!!

It's really unbelievable. My humble little blog has been hit 20,000 times! And the vast majority were not from me! Visitor number 20,000 is actually comes by frequently; he (or she) is from Montevideo, Uruguay! I would love to know more details about your PACS and your hospital. Drop me a comment below. Does your facility need a visit from Dr. Dalai? Send me a ticket and I'll be there!

I'm sure there are those out there that view me as somewhat of a terror, if I've even reached their threshold of attention. Well, maybe I'm more of a terrier than a terror...I sink my teeth into an issue and then I just won't let go. As I love my Jack Russell Terrier dearly, that's a compliment. Much more to come!

Thursday, September 14, 2006

Voice, I mean Speech Recognition, Buggy Whips, and OODA Loops

I love new technology. I live for it. I spend inordinate amounts of money on it, much to my son's delight, my daughter's bemusement, and my wife's chagrin. If there is an electronicomechanical way of doing something that I could have done manually, well then, I'm on it. However, when it comes to Voice Recognition, I do an about-face from my progressive side and become a pure Luddite. But follow my reasoning, and you might agree.

First off, the Wikipedia informs us that "Voice Recognition" is the task of recognizing people from their voices, and this might be done electronically for identification purposes, among other tasks. What we are really interested in is Speech Recognition which the Wiki says "is the process of converting a speech signal to a set of words, by means of an algorithm implemented as a computer program." Now, this has been one of several Holy Grails for computer science since the dawn of time.

SR should be great for radiology, given that our main product is the typed report that is based on our talking into a microphone all day long. The old timey approach was to have a human listen to all that blather and type a report into a typewriter (remember those?), or into some computer or another. Now, if I can get said computer to actually understand what I'm saying, we eliminate the middleman, or woman, i.e., the transcriptionist. But is the technology there yet? In 1968, the movie 2001: A Space Odyssey told us that we should have had conversant, artificially-intelligent HAL 9000's, as well as commercial space flight, a Hilton hotel on a space station, a moon base, and exploration of Jupiter as of 5 years ago. Oh well. We don't even have Pan Am anymore. But, we do have VR, I mean SR, right? Here's a citation from a Journal of Digital Imaging article out of Mass General by Mehta and Dreyer, et. al.:


Voice recognition--an emerging necessity within radiology: experiences of the Massachusetts General Hospital.

Mehta A, Dreyer KJ, Schweitzer A, Couris J, Rosenthal D.

Department of Radiology, Massachusetts General Hospital, Harvard Medical School, Boston, USA.

Voice recognition represents a technology that is finally ready for prime time use. As radiology services continue to acquire a larger percentage of the shrinking health-care dollar, decreasing operating costs and improved services will become a necessity. The benefits of voice recognition implementation are significant, as are the challenges. This report will discuss the technology, experiences of major health-care institution with implementation, and potential benefits for the radiology practice.

Great article, and it was written in 1998! The italics are mine, by the way. So here we are, eight years later; why isn't everyone using VR/SR?

The problem seems to be that the technology really isn't there yet. Matrad6781 posted this on an AuntMinnie.com forum, and it tells the story in a painfully accurate manner:

My problem with our voice recognition system is that commands that used to be triggered by the thumb on a microphone are now voice commands. Often the software doesn't recognize my voice and I end up having to repeat myself several times. That never happened in the "buggy whip" days. Throughout my department you can hear radiologists saying: "Defer report...defer report...DEFER REPORT, dammit!" or "delete that sentence, DELETE that sentence, delete that SENTENCE!" Also, when I say "parentheses" or "quote" or "paragraph", my transcriptionists know what I mean. This system actually types out the words "parentheses', "quote", "unquote", etcetera. How clever is this? Is this what is meant by artificial intelligence? I have alot of "canned" reports, both normals and intro paragraphs for MRI protocols, interventional procedures, etc. At last count, I had 150 such "normals." Before voice recognition, all I had to dictate was, "Normal MRI of the left knee" and the transcriptionists called it up from their macros and sent it for my electronic signature. Now I have to remember the name I gave the normal report (ProVox calls them "Macros") and enunciate it properly (so I don't get a "Normal chest" appearing when I said "Macro Normal CT Chest Enhanced". But it happens, all too frequently. And I have to always keep an eye on the voice dictation window, the way you would a toddler to make sure it's doing what it's supposed to and not getting into trouble. By the way, that window, even when minimized takes up valuable real estate from my PACS work station (and I have four monitors!) I'm always moving the window around because it's obscuring images or the worklist. Very inconvenient. The worst is when the system thinks that I (or someone in the background) uttered a voice command that is one of the "nuclear option" commands, like "finalize report", "delete that paragraph", "cancel report." Then, poof, five minutes of dictation are gone, just like that, and I have to start from scratch. Are you guys telling me no one else has experienced any of these problems? Is it just our manufacturer? Lastly, the voice recognition is so bad, that everything ends up getting deferred by all the radiologists to the transcriptionists, so that they can correct the errors before sending to the task list for finalization. So we have as many transcriptionists as before. Last point: We have some great transcriptionists who catch errors that a voice recognition system would never recognize. I used to get electronic notes like "You said LEFT in body but RIGHT in impression." Or: " You gave a measurement of 3.5 mm in the body, are you sure you meant "mm" and not not "cm"?" These folks have saved my butt many times. I'm kind of glad that the voice recognition dictations still go through them as a fail safe mechanism. Also, one of our transcriptionists makes really good carrot cake! Let's see a VR system do that!


The bottom line is that these very expensive systems (think hundreds of thousands of dollars) do not have human intelligence behind them. No, I'm not saying bad things about the programmers! It's simply that there is a very rich background to our communications, and no machine has risen to the level of understanding, or perhaps I should say intuiting, what we put into it. The left/right and cm/mm problems are good examples. I suppose you could program the machine to count how many times you say "left" and how many times you say "right", but then what? Should there be an equal number? Not necessarily. So what is a poor machine to do? The human transcriptionist can easily find the discrepancies of this sort, but a machine just can't do that yet.

What are the advantages of SR that make it worth the kind of trouble Matrad describes? I can think of only two: time and money. If all works well, the SR system can have a report available online the instant you sign off. That's a good thing. Which can be equalled or even surpassed by having an adequate pool of human transcriptionists on-line and ready to do their thing. But speed doesn't seem to be the main impetus in many places. Sadly, what SR allows is the shifting of work onto the radiologist. The transcriptionist's job is really two-fold: she (or he) commits to the screen what the rad has dictated, and then she edits out the errors that may have occured. SR can do a passable job of typing (if one trains it to one's voice for a very long time), but it just can't do the editing. Since the radiologist is ultimately responsible for the report, some administrative types have decided that the rad should do the editing as well! Wonderful idea, if you are trying to rid yourself of transcriptionists. Unfortunately, this adds a lot of editing time to the rad's day that he or she should be spending reading studies. Another poster, Jack (Dr. Death) Kervorkian puts it in these terms:
(S)orry guys, in my book - time is money. If I have to spend 20% of my time correcting reports and looking for content, syntax, grammatical and/or spelling errors, that is 20% which I am not productive. Furthermore, it now makes me not a radiologist, but an editor of reports. Just think, in an 8-10 hour day that amounts to an extra 1-2 hours of agonizing editing. I'd rather have a second set of eyes and ears - which know my dictation style to look over me. Can't tell you how many times a transcriptionist has saved my ass from looking stupid, with the usual 'right/left" errors, or at the 12th hours calling a CT scan an MRI scan.. Although voice recognition will catch spelling errors, it won't catch content, grammatical or syntax errors, as mentioned above.


So everyone loses in this scenario, except for the bean-counters who justify the expense and the pain to the rads with the savings in personnel. Just great. Those who support SR call those of us with doubts "Luddites" and "buggy whip makers". AuntMinnie member Frank Hartwick suggests that we stick to the principles of the "OODA Loop" for decision making such as this to keep from being left behind. OK, what's an OODA loop, you ask...is it like a Fruit Loop? Not quite, and it really is germaine to this discussion. Click on the diagram below to blow it up...
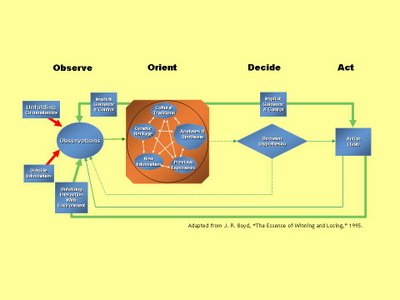

OODA Loop

The OODA loop (Observation, Orientation, Decision, Action) is simply a way to describe a decision-making cycle, designed by a retired fighter pilot, Col. John Boyd. Basically, it describes a dynamic process that one should go through to evaluate evidence and make choices, and how those choices are dependent on your background (even your "genetic heritage") and the information you get. The decision impacts your observations, changes your orientation toward the problem, and you remake your decision.

Got all that? So, I think Frank H's OODA loop tells him that SR gives good service and should be implemented. But MY OODA loop observation is that there are a lot of complaints about SR, and with my genetic heritage of worrying, and previous experiences of getting burned on buying some of the latest and greatest, lead me to the decision that SR isn't ready for me as yet, and thus the action of, well, inaction. I'm digging in my heels on this idea. I have told our administration that I and my group will not accept SR unless they promise us total human backup. In other words, if they want to spend $300,000 or so on a fancy microphone for me, that's just fine. As long as they realize that we rads refuse to become editors, they can go ahead and spend the cash. But don't wave the expenditure in my face when it comes time to replace some of the worn-out scanners that really need to go.

Am I really being a "Luddite" on this? I think not. My job is to interpret my studies, not edit the reports. No one has yet convinced me that SR technology has reached the point of really being ready for prime-time. And I don't make buggy whips...to really stretch the analogy, one could say we use buggy whips in our trade. SR could then be likened to an electric cattle prod, I suppose. But to carry this to its logical end, SR will eliminate the horse, and I'll be forced to use the cattle prod on myself! No thanks, guys. I'd rather walk.

ADDENDUM....

I just had to add this from a post from William Fife on the AuntMinnie.com thread...

For those of you who love VR here is something one of our physicians did one day on call. I will note that this physician had been using VR exclusively for MONTHS (a few words have been deleted (deleted) to protect the guilty). This is not a joke, this is an actual VR transcription of that the physician was saying (in bold).

Indicating this using (deleted). (I am dictating this using (deleted).)

Mr. date of 01/02 help recent films time.(Yesterday I went to help read a few films on my own time.)

A family cells. In some (deleted). there for over and out or.( I found myself stuck in some (deleted) error for over an hour.)

The year cannot: 5 hours report was (The ER kept calling to find out where the report was.)

This did not seem to encourage may help my colleagues and the films. (This did nothing to encourage me to help out my colleagues and read films.)


Today came in early to try again had.(Today I came in early to try and get ahead.)

Instead I am now line. Out of on the nodule was noted least 15 times. (Instead I am now behind. I had to run the audiowizard 15 times.)

I had to call the past / (deleted) to support. (I had to call the PAC/(deleted) support staff)

12 joules was helpful and white, there was nothing ET tube from home. He has new trials were to things year defects at myself. (While Joe was helpful and polite, there was nothing he could do from home. He asked me to try all sorts of things here to fix it myself.)

Spent there are might time to ingest fat rather than reading films. The CT scanner post I am not expected fixed fat.Lysis any different. (I spent an hour of my time doing just that instead of reading films. When the CT scanner goes down I am not expected to try and fix it myself. Why is theis any different?)

The patient or best served 1 international unit films not tried fixed (deleted) problems were transcribed unknown reports for distended noxious females. (Patients are best served when I read films, not try to fix (deleted) problems or transcribe my own reports or send obnoxious e-mails.)

Kilohertz it is line, we need better on slight support. (When it works, it is fine. When it doesn't work, we need better on-site support.)


ADDENDUM #2:

This was just posted to AuntMinnie.com by "breastguy", hopefully a mammographer, and I think it really seals the deal against SR:
I heard of one rad at a children's hospital in PA who was trying to get a lawsuit together against Dictaphone for their false claims about the product. Every so often our chief circulates examples of gibberish that was sent out and cautions us to look at what we are siging - but it still happens -- one major problem is there is no "undo" button or delay- once you hit sign report it is gone and as it disappears you see "clitoral history" fly by and there is no delay to catch it. The quality of the reports clearly suffers. And you cant say "known Carcinoma" it comes out "No carcinoma" -- I curse the Powerscribe apps people that spent days with us yet never called attention to possible pitfalls like this - they never pointed out the weaknesses- we had to stumble over them ourselves. Sure you can save the reports and review them later, or send every one to the editor (be sure to keep some transcriptionsits to edit) but I can tell you, in our large group , with editors, crap still gets sent out and ref docs gleefully call you up to say "Did you mean Clinical History instead of Clitoral History?" Certainly makes us look foolish. As far as it not understanding the instructions to call up a macro- it was driing me crazy! I solved that - instead of my saying "Mammo Heterogenous Normal Compared" I renamed it "Hubert Nancy Carol" Dense mammo is " Denise Nancy Carol" etc and so on for the many screening mammo macros I created- here it does save time.

I really think that's enough. Frankly, after looking into this, I'm inclined to say "NO SR" altogether. The machines seem to compound the possible errors, making the transcriptionist/editor's job that much harder. This is a really, really, REALLY bad idea.
Sunday, September 03, 2006

Thursday, August 31, 2006

Logmein al Carbonite


Periodically, a product comes to market that improves my life considerably. Today, I'll mention two such wonders.

LogMeIn, found at http://www.logmein.com, lets me and Mark the PACS Guru take care of a lot of computers in a lot of places. There are various services offered including LogMeIn IT Reach, which is the one we use the most. This advanced program gives me remote control access to the target machine, the ability to perform management functions (turn services on and off, for example, remote reboot, and even direct file transfer). There is a free version that just gives one remote control, pretty nice for the price. This system is secure with 256-bit encoding, and the best part is that it will automatically negotiate firewalls, with no need to fool around with port-forwarding and the like. LogMeIn also offers a "Rescue" product that doesn't require any software installation on the receiving end. There is even a new service called Hamachi which is "a zero-configuration virtual private networking (VPN) application. In other words Hamachi is a program that allows you to arrange multiple computers into their own secure network just as if they were connected by a physical network cable." LogMeIn just might put the networking guys out of business! Well, not yet. My little illustration is prompted by the Chinese-dish sound of the non-caps version, logmein...like chow mein, get it?

Carbonite (http://www.carbonite.com), like its namesake, is a protective shell of sorts. I had been looking for a way to back-up my computer onto some nebulous place on the internet, and Carbonite provides this. It works like a charm. Basically, one just installs the small app and it backs up whatever portion of your disk you specify, up to and including the whole thing if you wish. The price is pretty reasonable, depending on how long you contract for the service. Check it out!

Tuesday, August 29, 2006

Dalai PACS

I don't like to repeat gossip, but there is a rumor floating around that I am going to start my own PACS company.

It's true.

Film at 11.

Sunday, August 20, 2006

How Many Monitors?


How many monitors is enough? How many are too many? Is there a "just right" number, Goldilocks?

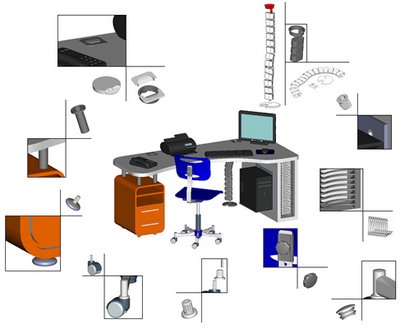
Probably, the answer differs for every radiologist, and every group. The 21 members of my group would give you a several answers. At home, most use just one commercial-grade Dell monitor for on-call prelims. (I, being different, have two, and a couple of my partners have just ordered out some used Barcos so they can do full interpretations at home.) At the hospitals, the majority of our stations have the 2+1 configuration: two high-res monitors and one 17" or 19" color monitor for worklist or 3D display. We still have several stations that consist of four high-res Barco monitors only. Now here is where opinions differ. Personally, I am satisfied with the 2+1 setup. I figure I can only concentrate on a small area of one monitor at any one time, so why have so much screen-real-estate that I can't look at immediately? Those who prefer the four-bangers (a legacy title I bring to this post from the old days of four-function calculators) counter that it is much easier to compare complex multisequence MRI's if you have more space to put the images. I guess that makes sense. The second reason, and the one that I find more compelling, is that when comparing CR's, it is helpful to view more prior exams at once, to better see trends in the patient's condition. That one makes more sense to me. This can still be done with a two-banger, but you have to cycle the priors on the second monitor.

I mentioned in a prior post that Agfa Impax 6.0 probably doesn't play well with an all high-res monitor set-up, so we will probably be adding a fifth, color monitor, to the four-bangers. We may need bigger desks, or maybe some sort of bracket suspension aparatus. Remember back when PACS was new, and some companies were showing the huge banks of 8 CRT's? Those were the days....


Image courtesy of http://www.ergodesk.de.

Another interesting discussion involves what should go where. Where should the new study go? Where should the priors go? On the far left monitor, on the far right monitor? This can and should be strictly up to the individual user, and with hanging protocols and presentation states, that should not be hard to, well, arrange. I've been hearing some talk about moving one particular series around, and that one has me concerned. Let's say you are looking at a complex multisequence MRI, and you wish to compare the current axial T1-weighted post-contrast sequence with its counterpart from last month's examination. The theory is that you should be able to move just that one prior sequence into a viewport or window that otherwise holds nothing but the current study. Personally, I have a feeling that could be dangerous. What if I get distracted, and somehow, in my reverie, forget that this sequence in the middle of the screen is actually from the old (here, the wrong) study? Disaster awaits. I know those planning to do this sort of thing are intending to put some fancy border around the foreign sequence, but will it be enough to penetrate my thick skull? Perhaps if the border had a flashing marquee that said "Danger Will Robinson, Danger, Danger!!" Personally, I want the ability to disable this function, although I guess I might come to like it someday.

You can sometimes teach an old doc some new tricks....

Wednesday, August 09, 2006

Anti-Semitic Radiology Residents???

I take the pulse of the world of Radiology via AuntMinnie.com. The Residents' Digital Forum is always lively, with discussions of topics ranging from politics to how to go about switching residency programs.

The political threads can get rather intense, with conservative posters (often called Neocons, Right-Wingers, Bushies) going head-to-head with liberal posters (Leftists, Socialists, Bush-haters, Commies). You get the idea!

Israel, Islam, Iraq, and the Mideast situation in general creates a flash-point for discussion. The usual polarization is present within these threads, but I have noticed a very ominous trend: there are now several blatantly anti-Semitic posts. Here is a thread about the current war between Israel and the Hezbollah in Lebanon. I won't even try to discuss the issues of the war itself here; that's beside the point I am trying to make. The AuntMinnie thread contains a considerable majority of anti-Israel sentiment: Israel is bloodthirsty, Israelis are the real terrorists, America is stupid for supporting Israel. Fine. But then come the racist rants: The media and Congress are Jew-run, Jew this, Jew that. It makes my blood freeze. You see, this forum is on a RADIOLOGY web-site, and is geared toward residents (although old farts like me drop in periodically.) These comments are ostensibly from intelligent young physicians! What has happened? I wish I knew. But I can only speculate. There is a lot of frustration out there, and a tremendous amount of anger, mainly on the part of the liberal posters anyway, about our involvement in Iraq, and about President Bush. I don't know if this is manifesting into anti-Semitic sentiments de novo, or just unmasking such feelings that were already there. Either way, the fact that supposedly smart people are rehashing material from the Protocols of the Elders of Zion (an anti-Semitic tome from years ago) makes me worry. A lot. What will happen to this country, and to Israel, for that matter, when this angry young generation comes of age and acquires real political power?

Those who hate destroy themselves just as much as the objects of their hatred. You might not be able to prove that scientifically, but it is so nonetheless. I hope these kids learn that before too much longer.

Wednesday, August 02, 2006

Edge Detection Rule(r)s!!


I haven’t posted much in the way of pure PACS lately, in my quest to be a politician and policy maker (or breaker as the case may be). My good ideas seem to be coming less and less frequently; must be old age, or stress, or some combination thereof.

Finally, my rusty steel trap of a mind has come up with something new. Well, it really isn't new, but it is a simplified and useful twist on an old concept.

Edge-detection is a well-known mathematical procedure, useful in the detection of abnormalities on mammograms, and nodules on CT's. There are a number of Artificial Intelligence (AI) programs out there that sniff out badness on these exams and do all sorts of measurements allowing for followup.

My idea is much simpler, and applicable to the everyday PACS world. In fact, it occured to me whilst measuring innumerable lung nodules on a cancer patient. It is a true pain to draw in short and long axes, especially when the nodule is in the subcentimeter range (and even more so when your non-averaGE PACS won't let you show more than one pair of measurements on the screen.) So, let's create an edge-detection-based ruler! As in the rather primitive mock-up above, the user draws a circle or ellipse around the nodule in question, and tightens up its radius to a reasonable level. The computer then takes over, detecting the edge of the nodule, finding long and short axes, and even giving average density, total area, etc. Yes, this could be expanded into 3D, seeking the nodule in the slices above and below, but that adds so much complexity, it probably isn't worth it. All I want is my measurements done for me without tedious submillimeter movements of the mouse. The Dalai Edge Detection Ruler would do the trick.

OK, which PACS company is going to make this happen? I'll take 50% royalties, thank you. Uh, how about 30%? 20%? Oh well, just put this in action and I'll be happy!

Sunday, July 23, 2006

The Idiot’s Guide to Writing a Letter Home…

Image courtesy of http://www.koretz.com


My son is still at camp, enjoying the 6th of 8 weeks away from Mom and Dad. Well, make that 7 weeks away, because I was up there in the North Woods myself a few weeks ago playing doctor.

My son is a bright fellow, but when it comes to writing home, well, we never get to see that brilliance in action. My daughter, who behaved exactly the same way when she went to camp, decided to do something about this behaviour, and she wrote the following:

We noticed you were struggling with the art of writing to your family, and so we thought we would include a sample of how the typical, loving, caring son, tackles this difficult task. First we will name the unacceptable forms of letter writing:

1. Empty Envelopes: Save yourself a stamp, an empty envelope says I’m thinking about you like (a friend of ours) says I have sympathy (In the dictionary, sympathy sits between sh*t and syphylis!)

2. Sending Food: Unlike at camp, this is not a hard to find commodity when at home. We have our own potato chips, thank you very much, but we do appreciate the offer!

3. Stick Figures: We are out of the Stone Age thank goodness! That means no loin cloths, no grunting, and NO picture writing!

Now that we have looked at the less than desirable forms, let us now examine the correct way to write a letter:

Step 1: The Greeting...Typically, a kind phrase or welcome is used here. This may include, but is not limited to the following examples: Dear Mom and Dad,Hey Family!What up, home dawgs?!Hiya Bubba, Bubba Senior, and Bubbette!

Step 2: The Summary...Usually following the greeting is an inquiry into the state of the family, followed by a description of one’s current state. Next, a list of activities, complete with details and opinions concerning the events, is given:
How are you? Camp is AWESOME! Today, I had a blast at canoeing- I portaged for 3.4 miles, using only one hand and blindfolded. Then, Bobby Joe and I went hiking on a nature hike, and caught a bear! We’re having a great time teaching it to dance and do tricks! I’m leaving to go on Isle Royal tomorrow- my pack weighs 150 pounds, so I think I might take my mattress and the toilet out of my pack so I can actually carry it!! I can’t wait to go on the trip though!


Step 3: The Wrap Up
Finally, after the letter is complete with information, you may gradually bring it to an end. The kind writer informs his reader he will soon be ending the letter, and uses a hope or promise (see example) to conclude:
Well, that’s all going on here! I hope that everything in boring South Carolina is going well! I promise to write again after Isle Royal with tons of stories about my trip!

Step 4: The Sign Off
This difficult skill is left out by sons at camps across America, however, it is one of the most important parts of the letter! Your family’s assurance of your well being lies in this lone signature. Typically, campers will precede this valuable information with an expression of emotion:

Love,
Jonathan

Luvya,
Jonny-Boy

Haven’t showered in a week- I smell,
Stinky

Sincerely,
Mr. Jonathan B.


Hope this helps your writer’s cramp! Can’t wait to hear from you soon!

Love,
Your Family

Wednesday, July 12, 2006

Virtual PET/CT: Dalai's Idea Validated!


I am often asked to lecture about PET and PET/CT to local groups, having ushered our state into the positron era. Of course, our state was the last to get a PET scanner, but I'm the one that brought it here! Anyway, my PET/CT lecture ends with the image above, a simulated combination PET/Virtual CT. Wouldn't it be nice if the bad stuff lit up like this?

I won't take credit for the idea, as I probably saw it somewhere. Still, I was thrilled to see a real demonstration of the concept in this month's Journal of Nuclear Medicine. In the article "Flying Through" and "Flying Around" a PET/CT Scan: Pilot Study and Development of 3D Integrated 18F-FDG PET/CT for Virtual Bronchoscopy and Colonoscopy by Andrew Quon, Sandy Napel, Christopher F. Beaulieu and Sanjiv S. Gambhir, from Stanford use a GE AW 3D workstation (oh well) to fuse a volume-rendered virtual colonoscopy (and bronchoscopy) to a volume-rendered PET. Here's the result:

Now, the paper and pdf versions of the article don't show the virtual fly-through, but I'll bet it's pretty spectacular. Great idea, huh?

Tuesday, July 11, 2006

You Don't Need PACS For This...


While playing pediatrician at camp, I encountered a couple of tick bites, several dozen sore throats and runny noses, and other joys of having 200 boys gathered into one place. At 10PM on my last night in camp, I got the call that a young man had hurt his toe playing basketball. When he was carried into our little infirmary by his pals, the abnormality was rather obvious. I chose not to reduce this lovely little dislocation without better drugs than I had on hand, so I sent him on to the neighboring city. Better for him to hate the ER doc than me! Ah, primary care.

Monday, July 10, 2006

America the Porcine

Image courtesy of http://animals.timduru.org
I just finished my stint as camp doctor yesterday, and we flew home last night. On the last one-hour hop from the hub city to our average town in the South, I encountered some behaviour that troubles me greatly. Delta Airlines' web-site would only allow me to book seats 10A and 11A, window seats, for my wife and myself on this regional jet flight. You know the planes, the ubiquitous CRJ 50 passenger jobs. I actually prefer them for shorter flights, and find them comfortable enough with 2 x 2 seating. I have never noticed any particular difference in the aisle seats, or the window seats. (You get a little more legroom in an emergency exit row.) I figured we might be able to trade seats once we got on the plane. Really, who would refuse to let a married couple sit together? As it turns out, the occupants of seats 10B and 11B did just that. These were well dressed and well-spoken people, who were travelling alone. When we very politely asked if one of them would be willing to trade, they rather coldly refused. It seems they MUST have the aisle seats on that particular plane, and, no, neither would consider sitting in the window seat. Both very smugly noted that they had selected their aisle seats online, and that was the end of that. My wife and I looked at each other and shrugged. The week before, when we flew to visit our relative with cancer, another passenger was making a fuss about wanting to sit by a window on the same hop. My wife and I agreed to sit separately on that occasion to accomidate this stranger. Apparently, what goes around doesn't always come around after all.
Have you tried to make reservations for much of anything lately? You will find that everything is snatched up as soon as it becomes available. We have become a nation of hoarders, more bluntly, a nation of pigs (which is an insult to pigs). We will shove anyone else out of the way to get our hands on anything we think we want or deserve. Our lives have become a big race to get to the goodies before the next guy, and make sure we get our share, and his too if we can manage it. This behaviour is not borne of need, simply of gluttony, greed, and entitlement. It is the same basic instinct that drives people to want their CT's when they want them, be it 3AM or 3PM, and the same motivation that keeps self-referrers self-referring. I guess it isn't unique to Americans, but we seem to be very, very good at it.
I have no answer for the implied question of what to do about our porcine behaviour. Perhaps if we keep in mind where bacon comes from......

Tuesday, June 27, 2006

Alternative Murder

Here's one from the heart, folks. Hold on to your hats.

I'm going to lose two of my relatives to cancer. That is sad, of course, but what is really unfortunate is that they could have been cured at early stages of their disease. What happened? They became enmeshed in the folly of "alternative medicine", and they are going to die because of that.

I won't name names or give any identifying information. One relative had cancer of the tongue that could have been excised and eliminated when it was quite small. He refused conventional therapy proposed by one of the leading cancer centers of the world, and instead used diet and supplements to treat himself, on the advice of a "practitioner" with barely a high-school education. Three years later, the disease advanced to the point that he had to seek conventional therapy, and he underwent a glossectomy. That's a nice word for having your tongue cut out of your mouth. He "eats" through a tube in his stomach these days.

The other relative has breast cancer. She and her husband, very smart and well-educated people, decided that nutrition and other alternative methods were the only treatment for her. A year later, this formerly healthy woman is an orange, jaundiced skeleton. She just had a biliary stent placed, and she can't even consider chemotherapy until she builds up her strength. Which she can't because she had starved herself trying to follow various cancer diets. My wife and I made an emergency trip to see this relative over the weekend, and she still doesn't realize what has happened to her. She fears most that the cancer has spread to her brain, because the local practitioner of ElectroDermal Screening told her it had done so.

People, I don't know whether to cry, scream, or what. How did this happen?

In the short space of one post, I can't properly cover the entire topic of alternative medicine. I strongly refer you to http://www.quackwatch.org. Dr. Stephen Barrett has spent the last 30 years examining the phenomena, and his articles are mandatory reading on this sad subject.

There is no single reason for people to suspend reason and go for the alternative therapies. Victims include rich, poor, educated, illiterate, black, white, Jewish, Christian, Muslim. No one is immune. The only common thread is that most people will be vulnerable at some point in their lives to the ministrations of charlatains, and those with a chronic or recently diagnosed illness are right at the top of the list. Why go through painful and debilitating chemotherapy when nutrition and electrotherapy can cure you of your cancer?

The "practitioners" usually have no scientific background, and learned their trade by weekend seminar, or perhaps right here on the Internet. Their idols, the inventors of the wonderous therapies, assure them with false testimonials and bogus science that their therapy works. Why are these miracles not accepted by the mainstream medical community? My relative with the tongue cancer was quite convinced that there is a conspiracy amongst all physicians, insurance companies, and pharmaceutical manufacturers to keep these "cures" away from the public, so we, the conspirators, can keep raking in the cash. Just take a look at this "infomercial" from Kevin Trudeau, who is revered among the alternative believers. He has since been banned from making such blatantly false statements. He was interviewed on TV recently, along with someone from mainstream medicine, and someone else from the alternative community. The mainstream doc lambasted him, and the alternative "doc" praised him. My relatives believed the latter.

In some cases, the victims of this deceit really do distrust the traditional medical community, and many are prone to believe conspiracy theories anyway. There is a very simple counter argument: Doctors and their families get cancer as often as any other group, and they live and die in the same percentages as everyone else. If there were some "secret" cancer cure, don't you think somebody would "break ranks" and reveal it to the public after all this time? Perhaps the greatest irony is that we are accused hiding and suppressing this stuff so we can make money. The quacks, however, are very quick to charge as much as much as they possibly can for unproven, untested, ineffective, and often harmful products.

Human beings are well known for believing what they want to believe, even when faced with heaps of evidence to the contrary. Throughout history, quacks, charlatains, witch-doctors, and all of their ilk have misled those who get caught up in their lies. It is no different in the 21st century, I am sorry to report.

Not being bound by the conventions of political correctness, I am going to call this what it is: MURDER. These criminals convince the naive to shirk medical treatments in favor of their patent medicine and snake oil. Many of the victims will die needlessly, and often horribly. That constitutes murder in my book.

Don't think for a moment that I am cannonizing the medical community. As you have noted in the pieces on self-referral, I think we need to fix a few things ourselves. M.D.'s are not above trying to make an extra buck, and I don't excuse them for it. But the methods we use for diagnosis and treatment have evolved via the scientific method. We do not think we possess the Absolute Truth, and we are constantly testing and retesting our diagnostic and therapeutic approaches. I am not ashamed to charge for what we do; we know we are offering the best we have, not something mired in secrecy and obscurity, and "proven" by handwaving and innuendo.

Again, I keep creeping toward more governmental intervention. The government MUST step in and stop this madness. People that make bogus claims need to be prosecuted. Those that have led their victims to their deaths should be up for murder. Because that's what their lies and deceit accomplished, the death of innocents whose only crime was believing the sales pitch. Perhaps there is a greater punishment awaiting these false practitioners, but for the moment, I'd rather trust the government to take care of these murderers. That's what they are.

Fifteen Thousand And Counting!

Image courtesy of http://aes.iupui.edu/
I thought it might be better to note visitation milestones a bit less frequently, and so we're now on the Q5000 scale.
Visitor 15K comes from London, Ontario, Canada, via Huron Telecommunication Cooperative, Limited. I will tell you that he (or she) was perusing an AuntMinnie.com thread, but I won't tell you which one. Believe me, we leave really huge tracks behind us on the web.
Thanks to all my visitors! You've made me what I am today...whatever that is!

Sunday, June 18, 2006

The Da Vinci Code
...or Opus Dei and the Knights (Templar)


I finally got around to taking my son to see The Da Vinci Code. At 12, he is a voracious (dare I say precocious?) reader, and after reading the book, he was quite anxious to see the movie.

Now, I don't want to spoil it for anyone, so both of you out there who haven't seen the movie or read the book STOP READING NOW!

OK. To summarize, the story involves several threads revolving around the premise that Jesus was married to Mary Magdaline, and she bore Him a daughter after the crucifixion. This certainly interferes with the concept of Jesus' divinity, and so the Vatican has tried mightily over the years to suppress this, whilst the Priory of Sion and the Knights Templar attempted to protect Jesus' descendants. Got all that? I'm really simplifying things here. The movie goes on to implicate a strict Catholic order, the Opus Dei, in several murders designed to quash the Priory once and for all.

There are probably a thousand web sites out there that dissect the arguments, and the "facts" of the movie in tremendous detail, and I won't even try it here. Suffice it to say that the movie is enjoyable in a plodding, mystery-story fashion, and it was fairly true to Dan Brown's book. I would recommend you read the book first to be able to follow the plot-twists.

The book and movie have caused great consternation, or at least a lot of discussion in the Christian community, and I can understand that. Coming from the Jewish viewpoint, I don't find the concepts particularly offensive. Judaism does not accept the divinity of Jesus in the first place; rather most of us consider Him to have been a great rabbi, perhaps the first Reform rabbi, and possibly a Prophet in His own right. You will notice very few bachelors among the Jewish characters of the Old Testament; it was tradition for the best and brightest to marry and have lots of children (be fruitful and multiply, as they say), and so it would not be surprising for a rabbi or great teacher to have done so. Think of this as the world's first eugenics program: you want to breed your best stock. I can only speculate as to why the Catholic Church took the exact opposite approach with their clergy.

I guess I can't comment with any great passion on how the "truth" as concocted in the Da Vinci Code would affect Christianity. Much evil has been done in the name of Christianity (the Inquisition, the Crusades, for example), but I would be so bold as to say that overall the good deeds over history outweigh the bad. Nobody is keeping score as far as I know. I realize that the divinity of Jesus is a fundamental tennant of modern Christianity, but even if it were not the case, His teachings would probably still be relevant. Basically, they were a softening of the fairly harsh version of Orthodox Judaism practiced in His day, and one could almost say that we Reform Jews are closer in spirit to what Jesus taught than anyone else. How about that?

I have tried and tried to tie this whole thing into PACS, and I'm coming up short. Maybe we could use the Cryptex to enter our passwords?

Sunday, June 11, 2006

Lessons from the Vasa, and Other Baltic Musings

The Vasa, courtesy of the Vasa Museum, http://www.vasamuseet.se
I'm back from Europe, and jet-lag is setting in to a significant extent. Before I drop, I wanted to post about some of the places we saw on our Baltic cruise.

Oslo seems clean, and modern in a timeless, Frank Lloyd Wright fashion, although the focal point of the city is the Akershaus Fortress, built in the 1300's. For some reason, I find the place very intriguing. Copenhagen had the feel of a much older city, with a feeling of age that we simply don't have in the much younger United States. Stockholm is somewhere between the two, and I found it my favorite of all the places we visited. Helsinki was rather stark, though it still has much of beauty, including a Lutheran church blasted from a stone hillock. Our time in St. Petersburg was rather surreal; a visit to Russia is still uncomfortable, even though the Russian Republic is now a democracy. Our guide spoke almost whistfully of the old Soviet era: it was hard, but the State took care of its people. I fear the old generation will have to pass on before freedom is totally accepted. The Russians are well on their way, however; there were many more Lexuses on their roads than I see here at home! Talinn, Estonia, was a surprise; there is a beautiful medieval city adjacent to a very modern metropolis. The Estonians recovered their freedom and statehood only 15 years ago, and they are fiercely proud of their new/old democracy. If only their weather was better! We ended our trip with a few days in London. We saw the major sites (Buckingham Palace, the Tower of London, Madamme Tussaud's, Harrod's), although we certainly didn't even begin to scratch the surface. London is horrendously expensive...at first glance, the prices are similar to ours here in the US, but those numbers are Pounds Sterling, not Dollars, and therefore everything is roughly double in price.

Oh, yes, before I forget...gasoline everywhere we went was going for about $7-8 per gallon. It was only about $2 or so in Russia, but our guide told us that salaries were commensurately low as well.

Our ship and the cruise line delivered us safely, and very well fed, but there were a few (but significant) glitches that I'll discuss in a later post directed at Royal Caribbean. Get out your bashing clubs, folks!

Delta flew on time, and they didn't lose any of our luggage.

Now, the story of the Vasa. The ship was built in 1628 on the order of King Gustavus Adolphus. On it's maiden voyage, it sailed into Stockholm harbor, listed over to one side, drew water in through open gunports, and promptly sank. The good news is that it was encased in clay at the bottom of the bay, and was nicely preserved for 333 years until it was rediscovered and raised from the depths. It is on display today in a huge museum built around it, a ghost ship returned from the dead. What happened? Here an analysis from the Vasa Museum's website:

In the 17th century there were no scientific methods of calculating a ship's stability. It was not uncommon that warships heeled over and sank. Their cargo - the guns - were placed relatively high up in theship, whereas merchant-vessels stored their cargo in the hold, ie inthe bottom of the ship. Instead of using calculations, the 17th century shipbuilders used so called reckonings, which recorded certain ship-measurements. However, the reckonings used in building the Vasa were intended for smaller ships with only one gundeck. The Vasa was built differently. She had two gundecks with heavy artillery (when the norm was to place lighter guns on the upper gundeck). The standard rules obviously did not apply here. Deep down in the Vasa several tons of stone were stored as ballast. They were meant to give the ship stability. However, the main reason for the Vasa capsizing was that the ballast was not enough as counterweight to the guns, the upper hull, masts and sails of the ship. In the inquiries after the Vasa disaster it was revealed that a stability test had been performed prior to the maiden voyage. Thirty men had run back and forth across the Vasa's deck when she was moored at the quay. The men had to stop after three runs, well before the test could be completed - otherwise, the ship would have capsized. Present was Admiral Klas Fleming, one of the most influential men in the Navy. His only comment to the failed stability test was "If only His Majesty were at home!" After that he let the Vasa make her maiden voyage.Who, then, were to blame for the disaster?

Admiral Fleming. Partly. He could have stopped the ship after the stability test. On the other hand, the ship was already complete and the king was waiting impatiently in Polish Prussia.

King Gustavus Adolphus. Partly. He was anxious to acquire a ship with as many heavy guns as possible. He had also approved the Vasa's dimensions and was keen to have her completed rapidly.

The shipbuilder Henrik Hybertsson. Partly. Although he built the hulltoo narrow, he was a skilled shipbuilder who had previously built manygood ships. His unexpected death the previous year just complicated matters.

The captain Söfring Hansson. According to a new theory the capsizing of the Vasa may be blamed on the captain. He sailed a brand new ship with open gunports. The Vasa sank when water gushed in through the lower gunports! It would have been wiser to test the new ship on her maiden voyage with closed gunports.However, the inquiries showed that no one could really be blamed for the disaster. The main reason being the insufficient theoretical knowhow of the period. The Vasa was something new - a military experiment. After the Vasa, many successful ships were built with two,three and even four gundecks. The shipbuilders learned from their mistakes with the Vasa and improved later designs.

Facinating stuff. In some ways, we can today be very thankful that the Vasa met its doom in this manner, because it otherwise would not have been preserved for us today.
So, what lessons do we learn, and how in the world does this apply to PACS? Well, the Vasa website was a little more conciliatory toward the king than our guide; apparently it is commonly felt in Sweden that the whole mess was the King's fault. Gustavus declared that the Vasa was to be built with too many gun-decks, which made it very top-heavy and unstable, and the Admirals and Captains, and everybody else had to go along. The King is the King, after all. So, this is what happens when someone bulldozes ahead, convinced that his (or her) way is the right way, and the experts and critics be damned. I'll grant you that it is unlikely that lives will be lost if one picks the wrong PACS system, but the point is that the building of a ship, or the assembly of a PACS system, should not hinge on the whims of one group that "knows what's best" for everyone else. Rather, such decisions need to be made by acquiring as much knowledge and expertise as possible. The ship, or the PACS, needs to perform its duties, but it cannot be weighed down by bells, whistles, or guns that would jeopardize its functions, even if the King, or the radiologist, or the IT folks demand it. Compromise, folks. And listen. Or somebody might be digging up the remnants of your PACS in 300 years.

Dr. Dalai Promises.....


A few months ago, I signed up to be a beta-tester for Intelerad's new IntelePacs InteleViewer, hoping they would consider me InteleGent enough to help them out. I guess I've been doing a little too much muckraking lately, as I received this letter from Rick Rubin, Intelerad's Executive VP for R&D:
I see you’ve signed up for our Beta program. I think that’s great, with one proviso (can you guess?). I wouldn’t be comfortable giving you an advanced copy of the InteleViewer if you’re going to write about all its flaws on your blog. Our goal for the Beta release is to get exposure and experience with different PACS systems and users out there but with limited exposure so that we can find out and resolve any major issues before releasing the product. So, it kind of defeats the point if you publicize those problems.

Once we’re in general release, you’re obviously free to do whatever you want, and hopefully we can live up to your scrutiny. But for the Beta program, do you agree not to publish information on the viewer?

OK, Rick, here it is in print (well, if you hit Ctrl-P, you'll have it in print): I promise to behave, and I will not reveal any details of your beta product. I have little more than my crediblity, since my rogueish good looks have long since left me, and no one has ever accused me of being the best radiologist in the world. So, yes, you can trust me.

Blogging is a little like being a real author, but I don't have to answer to anyone. Therefore, I have to be my own editor and publisher, but I get to say whatever I want to say. The major joy of this exercise is knowing that someone is actually reading my illustrious prose, but even so, my goal is to be more like the Today Show than the Jerry Springer Show. I would like to entertain and inform, but I'm not out to ruin anybody or any company. However, I am not going to sugar-coat a bad product. When I bash a product, it is out of frustration borne of using something that wasn't ready for primetime (or was poorly designed in the firstplace) but was released as a full production model anyway.

Don't worry, Rick, I realize that a beta test is a beta test, and I am gratified that YOU understand it as well. There are those who use paying customers to work the kinks out of their software (actually, Microsoft comes to mind on that one), and I don't have time for that when I'm trying to do my work. I cannot think of any other major PACS vendor that has taken this bold step of allowing a large number of interested users to help test and shape a new product, although Rick mentioned something to me about eFilm back in the good old days doing something like this.

I'm expecting great things out of Intelerad. I'll report on this product when Rick gives the OK.

Tuesday, May 30, 2006

PACS, the WIKIpedia, and other musings from the Baltic Sea

At this very moment, I am on a ship traveling up the east coast of Sweden en route to Stockholm. This trip required my son to miss his championship baseball game, but one of the other dads was kind enough to email us the results. (My son’s team lost, unfortunately.) The communications link went something like this: My friend emailed the play-by-play from the field via his Blackberry. The messages went to the Internet, which I picked up in my cabin, where my laptop is also connected to the Internet via satellite. Now my connection is running at dial-up speeds, which gets really frustrating, but, on the other hand, I’m really tickled that I can be on a ship (at that time headed toward Oslo) and get email from someone at a baseball field in South Carolina. Oh, Brave New World.

The Internet probably has done more to unite humanity than any other single factor in history, as illustrated by my little vignette. A more practical and useful example would perhaps be the Wikipedia. This is a collaborative effort, basically involving anyone who wants to participate, to catalogue the world’s knowledge. Anyone can write an article, and anyone can edit the Wikipedia. You do have to be prepared to back up your contribution with facts, and you must credit any photos you submit. I have made my mark on the Wiki by altering the paragraph on PACS architecture to include to concept of Web-based PACS. No doubt it will be edited further, but I feel I have had my 15 minutes of fame.

So far, we have been to Oslo and to Copenhagen. Both are spectacular cities. Oslo is a little more stark in some ways, but I found it to be more compelling. It seems to be overall a more peaceful place, but it’s hard to get much more than just a subjective feeling in a few hours.

Norway has a great deal of oil money from the North Sea fields, and it taxes its citizens quite heavily. Still, the Norwegians enjoy numerous benefits, including socialized medicine. They do have a co-pay for doctor visits, but there is then a major-medical plan that takes over if necessary. There is apparently a growing wait for some non-emergency services, but no one in Norway goes without health care. Period.

I have been a very loud opponent of socialized medicine for most of my career, but I am at the very early stages of thinking it inevitable. I look at the American system, and I see how it is being gutted and deformed and derailed by greed and fear, by self-referral on the part of some doctors, and by gluttony for unneeded services on the part of some patients. We cannot go on forever like this. When I hear about how well a system like that in Norway is working, I have to wonder if theirs is the right way after all.

Forgive my melancholy. It’s a beautiful night on calm seas. I’m going to enjoy it. Thanks for listening. Oh, and by the way, thanks for your ever-increasing readership of this blog. May isn’t even over, and it has topped all previous months for numbers of visitors and page-hits. Maybe I’m at least keeping you guys amused, huh? I’m very grateful for your interest, and I hope you feel your time here is well-spent.

Monday, May 22, 2006

Showdown at the PACS Corral

The second-place winners of the shoot-out at the OK Corral
A rather unusual event took place at the SCBT/MR (the Society of Computed Body Tomography and Magnetic Resonance if you didn't know) meeting last month. Six PACS vendors, Agfa, Amicas, Fuji, GE, McKesson, and Philips were pitted against each other in the first-ever PACS showdown. This is really a mighty feat in and of itself; getting six PACS stations and associated servers to all work at the same time is quite a miracle. I wonder who paid the electric bill.
Several vendors had engineering/apps types running their demonstrations, which consisted of performing a set of typical PACS tasks whilst under the gun. Amicas sent a physician who was very well acquainted with their product, and probably the best choice to show the world how their system works for its intended end users.
According the the Diagnostic Imaging article, there was no clear winner to this little exercise. Sadly, while some vendors (Amicas rep Barry Gutwillig was quoted in particular) wanted the results released, ". . . The vendors with more sensitive concerns. . .won this debate. To ensure a healthy participation at the next showdown, the SCBT/MR will not publish how the audience ranked each vendor." (Italics and implied disgust are mine.)
DI interviewed some of the attendees, and received various responses. Here's one from Dr. Dennis Foley, chief of Digital Imaging at MCW: "Dr. Foley. . . said that Philips, McKesson, and Fuji performed reasonably well in handling large data sets and doing relatively routine daily work. None of these companies, however, had well-integrated 3D solutions in their packages, he said. His nod went to GE for its hanging protocols, exam comparison, access to prior reports, and recovery from interruption." Ahem. It's clear that Dr. Foley hasn't used Centricity in the real world.
I am very disturbed about the "coverup" of the results of the showdown. Let's run an Olympic race and only report the results if the US wins. Obviously, one of the biG vEndors had a problem with how things turned out. Perhaps the small fry were more confident, or at least felt they had nothing to lose. Barry said it best:
“The society asked us if we wanted the results released, and we said yes,” said Barry Gutwillig, executive director of marketing and business development for Amicas. “We wouldn’t be here if we didn’t feel we could rank. I think it’s a testament to the vendors who are here and maybe more so to the ones who are not.”
With all this in mind, here is my advice for prospective PACS buyers: Do your OWN showdown. Either get a bunch of vendors to set up demos at your place all at once (or fairly close in time to each other so the details remain fresh), or get access to a web-based demo that will let you pound on their system at your leisure. I really favor the latter, as you can get a much better idea of how things work in your own hands. Vendors? Can you make this happen?
PACS interface preference is a very subjective thing. I like this approach, you like that approach. In this game, the second-place winner is in no immediate danger of extinction. Perhaps future showdowns can work from some additional metrics, such as: Does the damn thing work? Does it get in my way? Is the interface clean and usable? On second thought, those metrics are pretty hard to, um, meter, aren't they?
ADDENDUM
I received this comment, which is worthy of being moved into the post itself:
As one of the "big vendors" who was present at the show, we were also actually extremely irritated that the results were not disclosed, wherever we placed. This change in policy occured after we went on site. We may not participate again if that is going to be the way the showdown is run as it seems kind of pointless.We also thought the demonstration script was watered down from the original proposal and would have liked to have seen some of the original more challenging scenarios tackled.BTW: You have a minor inaccuracy in your article. You wrote that "Several vendors had engineering/apps types running their demonstrations". Actually, all of the vendors had a customer radiologist running their workstation. Some just seemed geekier than others.
I'm thinking this is from HBO/McKesson, by the way...
Now I wonder which vendor limited the tasks and then Got Excited about the results and as near as I can tell had them quashed? GEe, who could it have been?
OK, enough innuendo. If the folks at Centricity Central want to comment, I will publish their words here verbatim, just as I have for the Anonymous other Big Vendor. Well?

Sunday, May 21, 2006

Cool is for Losers!

My daughter just graduated from high school this weekend, and she will head to college in the fall, departing my sphere of influence. My son is finishing sixth grade, and will hang on to the Dad payroll for quite a while longer. It is his contemporaries that are starting to really worry me, the little 11 and 12 year-olds that shouldn't have a care in the world. Sadly, there are young kids in my son's class, boys as well as girls, that are incredibly concerned with what others think and say about them. It is very important to be "cool". These days, being "cool" involves not eating, not studying, not listening, showing no respect, and generally not doing anything they should be doing. The consequences of all this for these children's health are the most frightening aspect of the whole mess. When I hear a 12-year-old boy say that he can't drink a glass of milk because it might make him fat, I throw up my hands in horror. Enough is enough, people!

I propose a new campaign to fight this horrible trend, "Cool is for Losers!" When you get right down to it, being "cool" just means that you are doing stuff that makes you popular, but might not necessarily be smart or good for you. Starving yourself, smoking whatever, drinking, doing drugs, piercing various body parts, dressing like a prostitute, dressing like a convict (the droopy drawers look originated with prisoners who wanted to, ummmm, advertise their backside wares to fellow inmates), and so on and so on and so on. A real classy way to act, huh?

Why is it so important to be cool anyway? We've all been teenagers recently (ha!) and we all know the insecurities involved in that age group. To be accepted is more important than being healthy, or looking like a human being. But those whose entire goal in life is to be "cool" are more likely than not those who are petrified that they won't fit in with the "in" crowd. While they might make themselves popular with one tiny subset of society, they ruin their reputation with everyone else, and may cause irreparable physical or psychological harm to themselves. To put it quite bluntly, it is the "losers" that try so terribly hard to be cool, and conversely, the attempt to be "cool" can make these kids losers.

I'm no psychiatrist, and I can't begin to find the solution for all of this. However, sometimes just a catchy phrase will get things started. So, spread the word among the young folks in your lives: "Cool is for Losers!" It might actually make them think about the weird things they're doing, which is at least a step in the right direction.

Wednesday, May 17, 2006

Dalai Busts a Junk Faxer!
Well, Almost....


My fax line at home rang at 3AM the other day, naturally the night before I had to take call. It was a message from my friendly Junk Faxer, and I had received the very same fax about 10 times already. But when someone wakes me at 3AM unnecessarily, watch out!

Some rather brief research on the Junk Faxer's fax-back number disclosed that he is using Global Crossing, and that the long distance provider is a little Seattle company called Threshold Communications. I called Threshold, and was able to speak to Karen, one of their VP's. She was very kind and helpful, and promised to get my number removed from the Junk Faxer's list. But, no, she could not disclose the name of the faxer. And she had been receiving numerous calls from disgruntled members of the public such as myself.

Junk Faxing is illegal, as it turns out, mainly because unlike email spam, it costs money to receive a fax. Paper, toner, ribbon, they all add uup, you know. But some of these guys just ignore the law and keep on faxing. We, the victims have very little recourse. There are some services, such as FaxRecoverySystems, that will handle the prosecution for you. Send them a dozen or so junk faxes, they will do the research, file the claims for the illegal activity, and send you a check for $100 or so. It's probably a good deal, as the footwork gets complicated, but keep in mind that the fine for each illegal fax is about $1500. FaxRecovery is recovering more than faxes! As an aside, they had a message posted asking for information about the rather ubiquitous fax, and I supplied them with Threshold's number. Hopefully, I'll get some sort of reward, although not having the phone ring at 3AM is reward in and of itself.

I am no lawyer, thank Heavens, but I have to wonder if the other companies involved in Junk Faxing have some legal liability. The people at Threshold obviously know that they are providing services to a company that is doing something illegal, as well as distasteful. Why don't they refuse to do so? Karen gave me the clue: the junk faxer has about 300 numbers through their service, "but we only get complaints about 3 of them." Money talks, eh?

It would be unethical for me to suggest that anyone contact Threshold and tell them the error of their ways, or to put the fax number of the Junk Faxer on speed-dial and help tie up his lines, so forget that I said anything about that. But if there are any Threshold customers out there reading this, perhaps they could mention the situation the next time they pay their bill? Just a thought.

Saturday, May 06, 2006

Walk the Line (Placement)

Courtesy of ClinicalCases

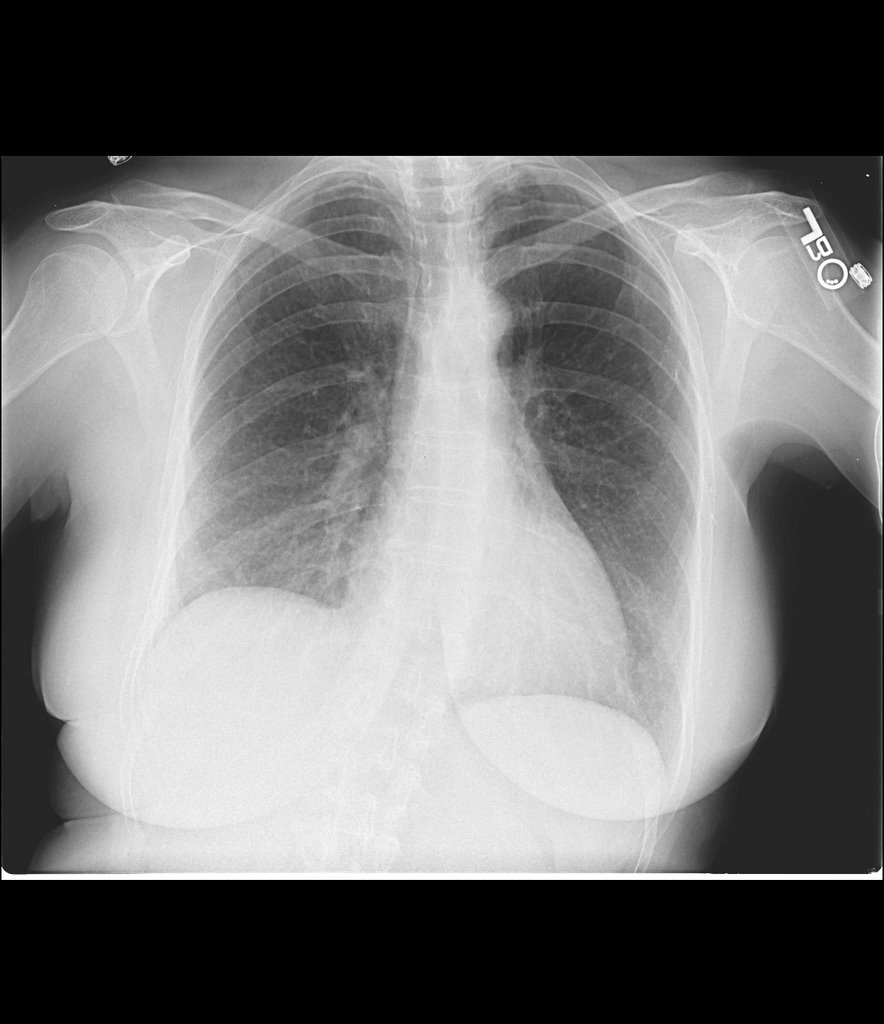
Of the many and varied annoyances we endure on call, the CXR for line-placement at odd hours is becoming more common. When a surgeon or internist places a catheter in a large vein, there are some potential complications that should be excluded with a radiograph of the area. These problems include a pneumothorax, hematoma, and aberrant course of the line. All well and good. However, some of our clinicians have gotten into the habit of placing the line, and then telling the nurse to get Radiology to "OK the line" as they walk out the door.
Now, I can exclude the complications outlined above, although if I'm working from home at 3AM, I don't have high-res monitors at my disposal, and I can't really confirm that there isn't a tiny pneumo. But even a Sony Jumbotron would not tell me if the line is "OK", in other words usable. That is a clinical determination. If there was good return of blood through the line at the time it was placed, then it should be usable from a hemodynamic (plumbing) standpoint. For this reason, I am now placing the following sentence in the impression of each and every study I read for line placement:

Function of the line cannot be evaluated radiographically. This must be determined by the presence or absence of blood flow at the time of insertion.

Now, the question becomes: is the clinician who placed the line responsible for looking at the post-procedure radiograph? I posted this question on AuntMinnie, and while there was some debate, the majority felt that yes, the clinician IS responsible. He/she placed the line, and will collect the fees for doing so. Line placement has known possible complications, and the clinicians are perfectly able to see these on the radiograph. Are we selling our birthright if we ask them to look themselves? I don't think so. Dr. "Sofa King" posted this on the AuntMinnie thread:

Part of the procedure for line placement in confirmation of positioning and excluding the presence of a pneumothorax. If you have not done this the procedure is not over. If you cannot do this you should not be performing the procedure. If you cant see the cathether traversing up the neck, you shouldn't be performing the procedure.


The ONLY purpose of these rediculous follow-up xrays for placement of anything in a patient is to spread or turn over liability. Don't kid yourself that it is for anything else.


That said, we are not asking them to interpret an xray. Like a stethescope and ultrasound (both of which most of these guys have in their offices) the xray is just another tool of the procedure. Don't think that the idea that you won't let these guys read things in the hospital will stop them from taking anything from you when they want. They have xrays in their office and they can easily take a one week course in anything and get credentialled.

Couldn't have said it better myself. We'll see how much trouble my little canned statement causes. For me, that is.

Teens’ Speech Patterns Often Fail to, Like, Demonstrate Intelligence


The "LIKE" phenomenon is taking over the nation. Kids today, mine included, cannot utter a sentence that doesn't include the word "LIKE". Fortunately, my kids respond to yelling, screaming, threats, and ultimately beatings, and their abuse of this four-letter word has abated somewhat. Sadly, "LIKE" spews forth as every other word from some of their friends, and that is NOT an exaggeration. I am at the point of not being able to understand these poor kids.

Somehow, I thought this was a new problem, but it seems that is not the case. Here is an article from the Columbus Dispatch dated 4/1/1998, written by William L. Bainbridge, who is Distinguished Research Professor at the University of Dayton and is President & Chief Executive Officer of SchoolMatch®, a Columbus based educational auditing, research, data firm:

One of our country's many talk show celebrities is CNN monarch Larry King. King has used his outstanding listening, questioning and communication skills to catapault himself into an exciting career as a premier television and radio interviewer.
In his spare time, the King of primetime question-and-answer shows has published several books focused on his communication secrets. In How to Talk to Anyone, Anytime, Anywhere, King advises his disciples not to rely on "nothing filler words." Words and phrases such as "you know," "as I said," "basically," "actually," "hopefully," and "whatever" are condemned by King as only slightly worse than "uh" and "um" in spoiling interpersonal communication.
Despite the best efforts of teachers and parents, the nothing filler word of the 1990's has been, and continues to be, the dreaded word LIKE. It must have started somewhere in a cheerleading camp and spread with rapid-fire speed through our schools with the help of the media beginning with the early 1980's song and movie, Valley Girl. The movie Clueless and its television adaptation currently being run ad nauseum on cable channels everywhere, unfortunately, presents an accurate picture of the misuse and overuse of this word.
Recently, our organization was conducting an "effectiveness audit" in an affluent suburban school district. The school system recorded incredibly high achievement in virtually all areas of the curriculum. During our team's site visit, we met with a group of community leaders including elected student leaders. The president of the senior class is an outstanding young lady with impeccable scholastic credentials. She has high scholarship examination scores and terrific grades. Her achievements and activities are most impressive.
After the session, several adults clustered in a private corner discussing this young person's "communication flaw," or what Larry King would call a "speaking tic." She seemed unable to speak more than five words without one of them being LIKE.
The session was videotaped. We reviewed the tape and, to no surprise, found sixty-four instances by actual count of this bright person cluttering her sentence with the word LIKE in less than four minutes: "You know LIKE I feel LIKE students LIKE have trouble LIKE selecting LIKE career awareness LIKE experiences." This student was given an opportunity to demonstrate her verbal skills before leaders of the community. In the minds of those in a position to help promote her aspirations, she undermined the serious concepts she was putting forward with a nothing word sentence splice. Moreover, her speech pattern seriously interfered with her attempts to discuss the issues and persuade the audience. What was she trying to accomplish? Had this tic been developed in the process of trying to be trendy with her peers? Some teenagers can turn this brainless language on and off at will. Others apparently have difficulty adjusting to the audience. Most are completely unaware of the extent to which listeners are irritated by this drivel.
Teens need to be encouraged to express themselves. But sentence fillers and splices, however, taken to an extreme, are not well-received in public presentations and interviews for employment, scholarships or college admissions.
If there is a parent or teacher of a teenager reading this who hasn't heard the LIKE phenomenon, consider yourself fortunate. For the rest of us, let's throw it out with the oral crutch "uh", "you know" and "like I said" of an older generation and try to promote better language skills and communication.

So, can we like stop this horrible like bad habit before we like kill somebody? Like DoctorDalai? Let's all like declare our homes like-free zones, so we can have some intelligent conversation, like we used to. You know?

Friday, May 05, 2006

California Legislature To Tom Cruise:
NO MORE ULTRASOUND!

AuntMinnie.com reports today on a bill in the California Assembly designed to thwart private individuals from buying their own ultrasound scanners for home use:


The bill (A.B. 2360) was introduced by Lieu in March. An amended version of the bill, dated May 1, states that violation of the proposed law would carry a criminal misdemeanor charge. The bill was slated for its third reading on the Assembly floor on Thursday.
"If someone sees Tom Cruise buy one, they think this is the thing to do. This is a public safety measure. There's really no medical reason for an untrained person to use this machine," according to Lieu (
E!Online, May 4, 2006).


Personally, I'm not sure how many private folks out there are going to cough up $100,000-$300,000 for their own private sonography suite. I also have to wonder whether the California legislature has anything better to do.

Now, we all know that Tom is really into Scientology, which spurns much of conventional medicine. I am glad to see him embrace some of our technology. You may know that Scientology uses a device called an Electropsychometer, or E-meter for short, to perform Auditing. Here is an image of the L. Ron Hubbard Mark-VII Super Electropsychometer:


Very impressive. From the Scientology website, we learn that:

When the person holding the E-Meter electrodes thinks a thought, looks at a picture, reexperiences an incident or shifts some part of the reactive mind, he is moving and changing actual mental mass and energy. These changes in the mind influence the tiny flow of electrical energy generated by the E-Meter, causing the needle on its dial to move. The needle reactions on the E-Meter tell the auditor where the charge lies, and that it should be addressed through auditing.

Couldn't Tom and Katie have just looked in on little Suri with one of these instead?

A Blast From The Past...
Vital Images Comes A-Callin'


Mark, our PACS guru, phoned me this morning with some interesting news: Carrie from Vital Images was on the line, and wanted to ask about updating our software licenses. Mark was rather confused, a very rare state for him, because he didn't know we even had any of Vital's products. I clasped my hands together in a sinister manner and slobbered with glee....

You see, we do own three Vitreas, dating from the mid 1990's. All are Silicon Graphics computers, two running IRIX (SG's flavor of UNIX), and one running Windows NT. These represent an investment of something like $150,000 to $200,000 or so. I wasn't involved with their purchase. Actually, if memory serves, the NT was a trade-in or something. But I digress.

About three or four years ago, one of the computers blew a hard-drive. I tried to nurse it back to health, but to no avail. So I called Vital Images. TEN TIMES! And I emailed them ten more times. Nothing. I posted nasty things about them on AuntMinnie.com. Nothing. We chalked up our losses, and went on to bigger and better things, like GE AW's and Siemens Leonardos, and various installs of Voxar 3D, all of which have done the job nicely.

I returned Carrie's call, and as nicely as I could for someone out $200,000 on non-working equipment, explained the situation. She had only just joined the service force, and was not happy to hear of our plight. I suggested she elevate the complaint to the president of the company, although that would be mainly for their benefit. Given this incredible service faux pas, I would not even accept a freebie at this point. If Vital wishes to donate a Vitrea to a third-world country in my name to assuage their collective conscience, that would be fine. But do tell them not to expect stellar service if it breaks.

Carrie promised to figure out what had happened, and to keep such a thing from happening again. I wish she had been with Vital a few years ago....

Addendum: The Vital rep for our area did indeed contact me, and we had a very good conversation. I do wish this new generation had been around when our problems started. Anyone want to buy a first or second generation Vitrea?

Sunday, April 30, 2006

The Case of the Missing Hole...
A Doctor Dalai Mystery

I'm on call tonight, and I've read about 200 studies since 8AM. Does wonders for the attitude. Imagine my joy (or lack thereof), when I received the following call from one of our hospitals:

"Uh, Dr. Dalai? This is Joe Tech from NorthSouth Hospital. I have another CT PA gram for you, and also a renal stone CT. Oh, and Dr. Feckless in the ER wants to know if we should scan a chest without or with contrast. Why does he want it? Well, he sees a hole in the lung on a chest X-ray, and he wants to scan it......"

Only the names have been changed to protect the innocent (ME!!!). The chest X-ray in question is anonymously reproduced below:

See the "hole"? It's in the region of the left axilla, and it is a bloody artifact caused by crossing of breast and arm shadows. Hole, indeed.

My response to Joe Tech was at first angry and then practical..."Is Dr. Feckless going to call in the surgeons based on the CT finding? No, don't repeat that....repeat the chest X-ray with the arms out of the way, and if the, ummm, hole is still there, THEN we'll do a CT." The repeat is found below. Voila! No hole!

This sad tale is wonderfully illustrative of how the ER thinks. Or doesn't as the case may be. The slightest twinge deserves the full court press. The slightest question is to be answered with a $1000 CT scan. In the middle of the night, of course. So, I have to get off my anti-self-referral bandwagon and get on my anti-scan-for-no-good-reason bandwagon. Hey, maybe they are the same bandwagon? Anyway, this knee-jerk ordering of a very expensive test is yet another reason imaging costs have skyrocketed out of sight. One of my partners very seriously states that the ER depends on us because we provide the diagnosis for them, because we have become so good at reading CT's, and because CT's have become so much better with multi-slice technique. Balderdash. The ER is just palming off their triage duties onto us. Order a scan of the affected area and see a few more victims while it's being done. And order scans on the new victims while we're at it.

This practice has got to stop, just as much as self-referral must be curbed. I keep backing into the conclusion that socialized medicine is going to do that for us, whether we like it or not. Hope I'm wrong. In the meantime, let me read the next 10 negative CT's.

Thursday, April 27, 2006

SCAR Capitulates to Estonian Pressure!


Big news in the PACS world, folks! SCAR, the Society for Computer Applications in Medicine has changed its name to Siim. Now, in theory, this stands for the Society for Imaging Informatics in Medicine. However, Dalai, your intrepid reporter, did a little digging and discovered the following: The Prime Minister of Estonia is, you guessed it, Siim Kallas! Coincidence? I think not. Notice in the photo below how Mr. Kallas (the one on your left) is looking quite pleased with himself, having just convinced Mr. Bush to move SCAR, I mean SiiM, headquarters to Estonia. I will actually be in Estonia later this year (really!) and I will check this out personally.

In the meantime, if you go to http://www.siim.com, you will reach the site of a plastics manufacturer with these featured products:


Looks like they are in the PACS business, too! Do you sense any takeover plans? Hmmmmm?