Thursday, April 27, 2006

United 93


Dalai's Note: David Beamer is the father of Todd Beamer, one of the heros of United Flight 93. His words are so eloquent and poignant, I have copied his statement from today's Wall Street Journal for the benefit of my readers. America needs to hear this, and we need to see this movie.

By DAVID BEAMER Wall Street Journal,April 27, 2006; Page A18

The calendar says it's April 25, 2006. At noon, my wife, Peggy, and I are walking around Battery Park -- near the Tribeca area -- in New York. It is our first time. The flowers are blooming; kids are fishing; people boarding the ferry to Ellis Island and the Statue of Liberty. Kids are laughing and noisy. The sun is shining. The vendors are hawking T-shirts, pretzels and some "designer" wares. And just up the street there is a hole in the skyline and in the ground.
In the park, there is a memorial with walls standing tall. Walls filled with so many names of those who gave their all in the Atlantic in World War II. How fitting that the names are here to honor those who gave their lives to enable this fun, this laughter -- on this sunny day. The sights and sounds of freedom continue.
Fast forward -- it is 10:30 p.m., April 25. We have just seen a movie premiere at the fifth annual Tribeca Film Festival. A film festival that has done so much to energize and revitalize the city, its people and especially the area that has that hole in the skyline and in the ground. This year the movie that had its worldwide premiere at the festival is titled "United 93." It is about the day when the hole in the skyline of New York was made -- the day when a hole was made in the side of the Pentagon near Washington, D.C. -- the day when a hole was made in a quiet mountain meadow in Pennsylvania. The day that our nation was attacked; the day when the war came home -- Sept. 11, 2001. The day our son Todd boarded United 93.
Paul Greengrass and Universal set out to tell the story of United Flight 93 on that terrible day in our nation's history. They set about the task of telling this story with a genuine intent to get it right -- the actions of those on board and honor their memory. Their extensive research included reaching out to all the families who had lost loved ones on United Flight 93 as the first casualties of this war. And Paul and his team got it right.
There are those who question the timing of this project and the painful memories it evokes. Clearly, the film portrays the reality of the attack on our homeland and its terrible consequences. Often we attend movies to escape reality and fantasize a bit. In this case and at this time, it is appropriate to get a dose of reality about this war and the real enemy we face. It is not too soon for this story to be told, seen and heard. But it is too soon for us to become complacent. It is too soon for us to think of this war in only national terms. We need to be mindful that this enemy, who made those holes in our landscape and caused the deaths of some 3,000 of our fellow free people, has a vision to personally kill or convert each and every one of us. This film reminds us that this war is personal. This enemy is on a fanatical mission to take away our lives and liberty -- the liberty that has been secured for us by those whose names are on those walls in Battery Park and so many other walls and stones throughout this nation. This enemy seeks to take away the free will that our Creator has endowed in us. Patrick Henry got it right some 231 years ago. Living without liberty is not living at all.
The passengers and crew of United 93 had the blessed opportunity to understand the nature of the attack and to launch a counterattack against the enemy. This was our first successful counterattack in our homeland in this new global war -- World War III.
This film further reminds us of the nature of the enemy we face. An enemy who will stop at nothing to achieve world domination and force a life devoid of freedom upon all. Their methods are inhumane and their targets are the innocent and unsuspecting. We call this conflict the "War on Terror." This film is a wake-up call. And although we abhor terrorism as a tactic, we are at war with a real enemy and it is personal.
There are those who would hope to escape the pain of war. Can't we just live and let live and pretend every thing is OK? Let's discuss, negotiate, reason together. The film accurately shows an enemy who will stop at nothing in a quest for control. This enemy does not seek our resources, our land or our materials, but rather to alter our very way of life.
I encourage my fellow Americans and free people everywhere to see "United 93."
Be reminded of our very real enemy. Be inspired by a true story of heroic actions taken by ordinary people with victorious consequences. Be thankful for each precious day of life with a loved one and make the most of it. Resolve to take the right action in the situations of life, whatever they may be. Resolve to give thanks and support to those men, women, leaders and commanders who to this day (1,687 days since Sept. 11, 2001) continue the counterattacks on our enemy and in so doing keep us safe and our freedoms intact.
May the taste of freedom for people of the Middle East hasten victory. The enemy we face does not have the word "surrender" in their dictionary. We must not have the word "retreat" in ours. We surely want our troops home as soon as possible. That said, they cannot come home in retreat. They must come home victoriously. Pray for them.

Wednesday, April 19, 2006

Happy Birthday, Dr. K!


Nobody escapes the Spanish Inquisition, or Doctor Dalai when he has photos!

Dr. K celebrated his 40th birthday by trucking into the hospital at 4AM to do a lumbar puncture on a 350 pound lady who wouldn't hold still. The day did improve significantly, and we had a chance to celebrate a little. Dr. K is an avid biker, occasionally riding all the way to the hospital from home. We thought he needed something a little snazzier......

8G SCAM!
A Public Service Announcment from Doctor Dalai

From the "if it's too good to be true it probably isn't" department.....
I troll around eBay periodically, looking for bargains and whatnot. I stumbled across a listing for a "Sony Micro Vault 8GB USB Flash Drive," going for only about $40. I immediately bid on it. Fortunately, a kind soul informed me by email that Sony doesn't make any drives that large in that form-factor, and what I was bidding on was likely a fake. I was able to withdraw my bid in the nick of time. Yes, it would look like an 8GB drive to my computer, until I actually tried to write something to it and read it back. Then its real size of 64 MB would become apparent.
In the interests of Karma, I am passing this information on to my loyal readers. For more information, please see this notice on eBay.
This has been a public service announcement brought to you by Doctordalai.com. Thank you for your attention.

Sunday, April 16, 2006

Happy Easter from Doctor Dalai!


I swear this has not been retouched save to eliminate the name of the store manager. I have always been one to promote good relations between peoples of all faiths. We purchased some Easter Chocolate for some friends, but we didn't realize until we left the store just how ecumenical our selection really was. I wonder if my friends will go for the ears first......

Saturday, April 08, 2006

The X-Ray Man


It’s 2 AM on a Saturday
The regular crowd is all here
There’s an old man yelling out at me
With dementia he’s had for three years

He says, “Doc will you give me an enema?
You know where the barium goes
I got cramps and the trots
Which I didn’t have lots
When I had a younger man’s hose…”

Oh La La La De De Da
La La, De De Da Da Dum

Read us a film, You’re the X-Ray Man
Read us our film TONIGHT
‘Cause we’re all in the mood for a malady
And CT will make us alright

Now John down in Nukes is a friend of mine
He tries not to wake me ‘till 3
And he’s quick with his V/Q
And then he won’t seek you
Till the ER just won’t let him be
He says, “Doc, they just ordered another one”
“I tried not to do it till 10…
But the patient is dusky and comatose
And probably won’t live until then.

Oh La La La De De Da
La La, De De Da Da Dum

Read us a film, You’re the X-Ray Man
Read us our film TONIGHT
‘Cause we’re all in the mood for a malady
And CT will make us alright

Paul is our CT Technologist
Who scans like he’s been there for days
And he’s talking with Davy whose CR’s are wavy
But they all pass QC anyway.
And the ward-clerk is practicing medicine
As the waiting-room slowly gets mean
Yes, they’re sharing a drink they call Thunderbird
Which does wonders for liver and spleen

It’s a really slow night for a Saturday,
I’m 63 studies behind
It takes more than my best
To read neck, head, and chest
And abdomen, pelvis, and spine

And the PACS system smokes like a chimney
And the Dictaphone squawks in my ear
And I sit in my chair and stare off in the air
And say, “Man, what am I doin’ here?”

Oh La La La De De Da
La La, De De Da Da Dum

Read us a film, You’re the X-Ray Man
Read us our film TONIGHT
‘Cause we’re all in the mood for a malady
And CT will make us alright

Saturday, March 25, 2006

Radiology, PACS, Clinicians, and Rocket-Science

"semila" started an AuntMinnie thread with the following posts:

Has anyone other than me concluded that the PACS market in general has become a big yawn? The conversations on these boards has deteriorated into techie minutia and nothing exceptional has come from any of the major PACS vendors in recent years. Price erosion continues to dampen the market and no new entries have come into the space in the past couple years. PACS has become a "cog in the wheel". Digital Imaging will in most cases now, be sold with larger information systems and will be a module that can be "turned on or off". PACS is not radiologies baby anymore, but one of the many niches that will make up the EMR/EPR. Aunt Minnie would be wise to diversify the content of its site to begin including more foward thinking discussion.

and

. . . PACS genrerally has one purpose: receive images from modality, compress, store, display and distribute. This isnt rocket science folks, and other industries do this all the time, they just dont have to answer to HIPPA! The foward thinking focus here should be how PACS fits into information systems. The small markets adoption of PACS is irrelevant.
Another note: I for one am a fan of image interperetation being taken away from radiologists and infused into the doctorate programs of the "real" docs, like cardiologists. Doctors that sit in dark rooms or in front of computers providing varying degrees of experience in diagnosis without ever actually seeing a patient is beyond me (teleradiogy - ugh). I am sure I touched a nerve with this one, but c'mon.........really. How bout this Dalai Lama cat.........this guy sounds more like an IT person than a doctor. Scary.

OK, Semila, you did indeed get my attention! I posted a more limited answer on AuntMinnie due to restrictions on the size of individual responses, but here it is a bit more fleshed-out.

Gee, where do I begin.... First off, I'll take the IT comment more as a complement than anything else, although I am no doubt considered a "scary cat" by both IT and physician camps. I'm in progress on my next AuntMinnie article concerning this particular relationship, and it is guaranteed to touch some nerves. As it turns out, I have degree in Electrical Engineering, major in Bioengineering, minor in Computer Science, so I do have the ability to “talk the talk” of IT, and occasionally even to “walk the walk”.


I tend to agree with semila to some degree about the level of "rocket science" or lack thereof in PACS. It has indeed been commoditized and often just comes as an added bonus with a suite of scanners or other computer systems. Rather like a prize in a cereal box. As an engineer, I do keep in mind that PACS at its core is simply the movement of image data from place to place, and this is not “rocket science” in this day and age. Semila points out that HIPAA plays a major part in its function, but as I found in researching my last article, one can use HIPAA as a template, and not hide behind it to avoid doing your job as some IT folks are wont to do.

At this point, I am going to throw in something so obvious, yet so obnoxious, that it will certainly generate some nasty commentary. So be it….. PACS EXISTS for the radiologists. Ha! Try to disprove that. As Pacs_Guru says, we radiologists are now blind without IT, but IT has no reason to exist without us. PACS defines how I do my job, which is to interpret radiographic and related imaging studies. Without PACS, the patient would still get the study and get it read, but this process would utilize film or perhaps reading directly off of the scanner’s monitor. There is a lot of technical jargon involved in the processes of “receiv(ing) images from modality, compress, store, display, and distribute”, even if it is pretty mundane. Those of us who come here are interested in these “boring” things, and they need to be discussed.

No doubt there will be eventual incorporation of PACS into the wider information systems; we are seeing that already to a minor degree. But since PACS is a tool for radiologists, I will push the very biased view that its next evolution/revolution needs to be in radiology workflow. I have only a vague idea, personally, of where that needs to go. When I went into private practice, 16 years ago, the work model was not so very different than it is today. We would pile in at 8AM, grab 20 or 30 jackets off a stack of 100 or so, put the films on the viewer, interpret them by dictating into a tape-recorder, with demographic information, history, etc, from a paper requisition, take the film down, sack it, stack the jacket, and then do the same for the next patient. The workflow today is to some extent an electronic version of the film days. We sign on to the PACS, select the appropriate worklist, queue up the first study, dictate it into the tank (eventually to VR), using demographics gleaned from the HIS/RIS system, and push the button removing this exam from the list and queuing up the next. (The sweat-shop/factory analogy is apt much of the time.)

The real difference between film and PACS is that we can manipulate the images we view, and in the case of multislice CT, we can add a number of tools to the armamentarium, including cine-view and the various flavors of 3D such as MPR, Volume Rendering, Virtual Endoscopy, and so on. At some point, there will be some radically different paradigm for reading, although it would have to go hand-in-hand with advances in imaging technology as a whole. We are already seeing that to some extent with whole-body CT. Instead of an X-Ray here and there, our patients are being scanned from head (almost) to toe. There is a great push in this direction from the ER, which wants us to do all their diagnosis for them. Thus, our trauma center often orders “Man-Scans” including CT’s of the head, neck, chest, abdomen, pelvis, total spine, at least one extremity, CT PA gram, and CT Aortogram. One stop shopping, folks. Much as I resent doing the ER’s docs’ thinking for them, I realize that this is where we are in 2006, and somehow my workflow needs to incorporate this monster. Here is where a good, unobtrusive PACS system can help me. All of the imaging needs to be delivered to me in a way that I can read it as efficiently as possible. How about the exams that benefit from 3D (Aortogram, spine CT’s, etc.) being automatically displayed with the MPR’s or VR’s necessary for rapid interpretation? How about automatically displaying relevant priors, images, lab data, etc? That is just the tip of the iceberg, and there are many folks much smarter than I am out there working on all this.

Semila proposes that radiologist need not be the masters of imaging, that other specialties could do at least as well at it. I’m trying very hard not to take this as an attack on my profession, but that is quite difficult as you might imagine. I am assuming that
semila is not from the US based on his/her diction, and perhaps things are different is his/her native land. I cannot put it better than did James P. Borgstede, M.D., head of the ACR, in his article “Chipping Away at Imaging” in this month’s Journal of the American College of Radiology:

One of the first canons radiology residents learn when they enter training is to look at the entire image. We are taught that this precept separates us from other physicians who view, but do not interpret, images. Image interpretation, as we all know, is difficult. Sometimes we’re given histories, and occasionally, we even have the opportunity to talk with referring physicians to assist us in our interpretations. Both written histories and dialogues usually focus on clinicians’ suspicions from their histories and physical examinations, assuming they have performed them. Clinicians direct our attention to parts of images or to certain organ systems. By adhering to the first tenet of radiology, we avoid missing unsuspected, but significant, findings included in studies. How many times is a computed tomographic scan requested for pulmonary embolus only to find that the patient has a rib fracture or subdiaphragmatic process that accounts for his or her symptoms? Radiologists, looking at the entire image, hopefully detect the significant abnormalities that are commonly missed by our clinical colleagues only looking at the portions of the studies piquing their clinical interest. These nonradiologist “viewers” of images mentally chip away at imaging examinations, excluding the areas they perceive as irrelevant. By viewing examinations with tunnel vision, they miss significant observations. It seems today that chipping away at images, and in fact our entire specialty, is an avocation of many individuals and groups inside and outside of medicine.Clinicians are keen on focusing on the parts of images within their specialties or subspecialties. Computed tomographic scanners have even been created to assist them in carving away unwanted portions of images. Cardiac imaging is one example; scanners have been created that remove everything from images except the heart. Therefore, physicians focused on the cardiac portions of scans do not have responsibility for the distractions created by bones, soft tissues, lungs, and other mediastinal structures. The companies marketing such scanners emphasize to nonradiologists the freedom from liability and responsibility such scanners create: “If you can’t see it, you don’t have any responsibility for it.” The companies in turn market the same products to radiologists under the pretext of protecting radiology for radiologists by excluding the ability of others to view portions of images that, in the companies’ opinion, are the purview of radiologists. What a help these companies are in chipping away at the images! Unfortunately, patients suffer in this scenario because they may require repeat scans to look at the structures excluded from the original examinations.

The point is that radiologists are trained for many years to interpret the entire image. Remember, what we are looking at is ultimately the anatomy and pathology, not just an image of shadows and density distributions, or water mappings, or areas of glucose uptake. The total yield is definitely more than the sum of the parts here. It doesn’t matter if they are reading a film, a digital image, or holding the patient up to the light. That is why the “old” radiologists are just as good at the new modalities.
Could you train a cardiologist to spot a lung cancer on a coronary CTA? Could you train an orthopedic surgeon to see that same lung cancer on a thoracic spine series? Probably. These folks are very smart and dedicated to what they do best. I mean to take nothing away from them. But where does this mentality stop? Why shouldn’t the surgeon look at the cytopath slides from his biopsy? Maybe he should supervise anesthesia as well? I’m sure he could be trained to do so.

Rather like pathologists, radiologists are impartial arbitrators. We have nothing to gain by coming to one conclusion or another. Once the study is ordered, we have only the goal of finding the right answer. We cannot, by definition, self-refer, which is NOT the case with clinicians. I’m not going to rehash that issue on this thread, but it may well be the one single reason NOT to turn over the reins of imaging to the clinicians.

Definitely a fascinating discussion, semilla! Thanks for starting the thread.

Thursday, March 23, 2006

TEN THOUSAND HITS for DoctorDalai.com!!!


TEN THOUSAND HITS!!!

Wow. Who'd have ever thunk it? From an inasupicious beginning to one of the four or five premier PACS blogs on the Internet! Of course, there are only about four or five PACS blogs on the Internet, so perhaps the competition isn't terribly fierce. Still, it's a monumental achievement as far as I'm concerned, and I thank all of you out there who have hit the reload button all those hundreds of times.

Anyway, I know visitor 10K quite well; he comes to us from mid-Florida via Road Runner, and he is one of the Mark's who define PACS for me. He knows who he is. Hey Mark, have you been sitting by the computer waiting for the opportunity? Did you think there might be a prize involved? Well, drop me an email, and you will qualify for an autographed photo, suitable for framing, target practice, or wrapping fish. Congratualations!

The Dalai PACS system is in progress...we have signed papers and promised money, and the equipment should start to arrive. The PACS adventure is just beginning!

Sunday, March 19, 2006

Impax 6.0: Glitch Report

I think Agfa may already know about this, but putting it on the blog guarantees that everyone who matters from Mortsel to Massachusetts will get to see it.

You will perhaps remember the monitor configuration screen:


Well, Windows has its own monitor configuration screen, accessed through the "Display" control panel. One of our stations was set up such that monitor 3 was between 1 and 2...it's just the way the cables ran. Windows lets you move the icon representing the monitor to wherever you want it to be, thus matching the physical configuration. Unfortunately, this totally confused Impax 6.0, which tried to place the image panes between monitor 3 and 2. That didn't work very well. After an hour of reinstalling video adapter and monitor drivers (at one point, I rendered the whole station useless and had to LogMeIn into it to get it to work), I just swapped the cables to the offending monitors, and redid the Windows Display setup. Voila! All is well. Maybe Impax 6.5 will take its cues from Windows, rather than attempting to override it. Remember, folks, the market has chosen Windows as the platform of choice; things go more smoothly if we let it do what it wants to do.

Saturday, March 11, 2006

Feature Fatigue and Lego PACS


Images courtesy of PC Magazine.


Even a blind pig occasionally finds an acorn, or even a truffle. So it is with yours truly. I was listening to NPR's "Weekend Edition" this morning (yes, conservative ol' Dalai listens to Radio Dark Side on occasion), and I caught an interview with Dr. Roland Rust from the University of Maryland. Dr. Rust holds the David Bruce Smith Chair in Marketing at the Robert H. Smith School of Business at the University of Maryland, where he is Chair of the Marketing Department and is Executive Director of the Center for Excellence in Service. Good credentials, right? Dr. Rust discussed the theory of "Feature Fatigue", and I was reminded instantly of Lego PACS. It seems I stumbled onto the same basic idea as Dr. Rust and his colleagues. The abstract of his recent paper tells the story:


As technology advances, it becomes more feasible to load products with a large number of features, each of which individually might be perceived as useful. However, too many features can make a product overwhelming for consumers and difficult to use. Three studies examine how consumers balance their desires for capability and usability when they evaluate products and how these desires shift over time. Because consumers give more weight to capability and less weight to usability before use than after use, they tend to choose overly complex products that do not maximize their satisfaction when they use them, resulting in “feature fatigue.” An analytical model based on these results provides additional insights into the feature fatigue effect. This model shows that choosing the number of features that maximizes initial choice results in the inclusion of too many features, potentially decreasing customer lifetime value. As the emphasis on future sales increases, the optimal number of features decreases. The results suggest that firms should consider having a larger number of more specialized products, each with a limited number of features, rather than loading all possible features into one product.

In the interview, Dr. Rust used the example of the latest BMW, which uses a technological innovation called "iDrive". This is sort of like a mouse for the car, and controls about 700 different functions. It looks good on paper, and in the showroom, but it seems that about 95% of those who buy the car actually use maybe 10 or 20 of those 700 options. To me, the way Lexus designs its dashboard is the antithesis to the BMW approach. It is simple and clear, there are far fewer buttons, but those that are there do what they are supposed to do superbly well. The car becomes almost transparent; it's just me and the road. But I digress. The bottom line is that people are attracted to products that have a lot of features, but usually, they end up not using most of the features that caught their eye in the first place. Hence, "feature fatigue", if not outright buyer's remorse.

I think this applies perfectly to my "Lego PACS" concept. Many systems out there are incredible technological tour de forces, or is that tours de force? I have written in my RSNA reviews about some of these. I will certainly give them great credit for innovation and the delivery of power to the end-user. However, do I really need the ability to change the wording of a 3rd-tier sub-menu? Does that help me get through my electronic stack of films any faster and easier? Personally, I think not. When I sit down at my station for a 6-hour uninterupted reading marathon, what I need (besides a bedside commode and a refrigerator) is the ability to interface with the study. I need the most streamlined, but still powerful, set of tools available to examine the image set, process it further if necessary, annotate it if necessary, and then send it away to be replaced by the next victim's, I mean patient's images. As I have put it many times before, the PACS should not get in my way.

I have yet to find an absolutely perfect system, but I still stubbornly insist that Amicas LightBeam comes close. I have the majority of what I need and very little of what I don't need. I do sit on the Amicas Advisory Committee, and I will do my best to keep them steered in that direction.

In the meantime, you'll have to excuse me. My cell-phone/PDA/MP3-Video player is ringing, and I seem to have misplaced my Bluetooth headset with caller ID, so I don't know who in the world is calling. Sometimes, I like feature fatigue....

Friday, March 10, 2006

Agfa Impax 6.0, Online!

Well, it's actually here and running. My friends from Agfa and Mitra have been very active on my blog today, with lots of hits on my older 6.0 postings. Now that I actually have it in my grubby little paws, so to speak, it's time for an update.

Our Impax 6.0 Interim Web Solution is a somewhat limited installation, as an appendage, if you will, to the Impax 5.2 system. One can query the database (but reports are not available), and "live" images must be pushed to the 6.0 server. Still, it is here and it works, and it is significantly better for home use than the venerable old Web1000.

Loading it was pretty straightforward, although on two of our machines, I ran into .NET problems. Impax 6.0 uses .NET 1.1, although Microsoft now offers version 2.0. One of the 1.1 hotfixes wouldn't install on my laptop, and I ended up reloading Windows. Likely the problem was with a virus scan or some such thing, and turning off the virus scan on the other problem machine let the hotfix load properly. Oh, well, my laptop needed housecleaning anyway. Once .NET was in place, the installer had to be restarted to load Impax 6.0, which then proceded nicely. One does need to know the address of the server during the install, a minor difficulty.

When everything is tidily loaded and rebooted, you click the icon to activate the program, and you are then greeted by this sign-on window:


I like the graphics, personally. I guess someone in Waterloo plays "The Sims" a lot, because the image sure does look like a Sims-esqe radiology department. Hey, it's cute!

To digress a little before we get into actual usage, you can customize several factors by hitting the Configuration toggle on the front page. For most, the only item that will change is the screen layout. At home I have two monitors, but most of my partners have one, and you can set up the program to do it your way on each station where you have logged in. You get to choose where the worklist goes, how many and which screens actually get the image data, etc, and it will remember the next time you sign in. Also on this configuration screen can be found just about every other control that used to live in the IMPAX Configuration (or Conflaguration as one of our PACS admins puts it) control panel. The new Configuration screen looks uncannily like the old control panel. Anyway, about the only other control a lowly end-user like me will use will the the RAM allocation. This program wakes up hungry, and will reserve just about all available RAM for itself. Fortunately, you can tone this down, and on my 4 Gb machine at home (ain't the Dell Outlet site wonderful?), using only 2 Gb seems to work OK, and allows Amicas LightBeam to operate simultaneously as well.


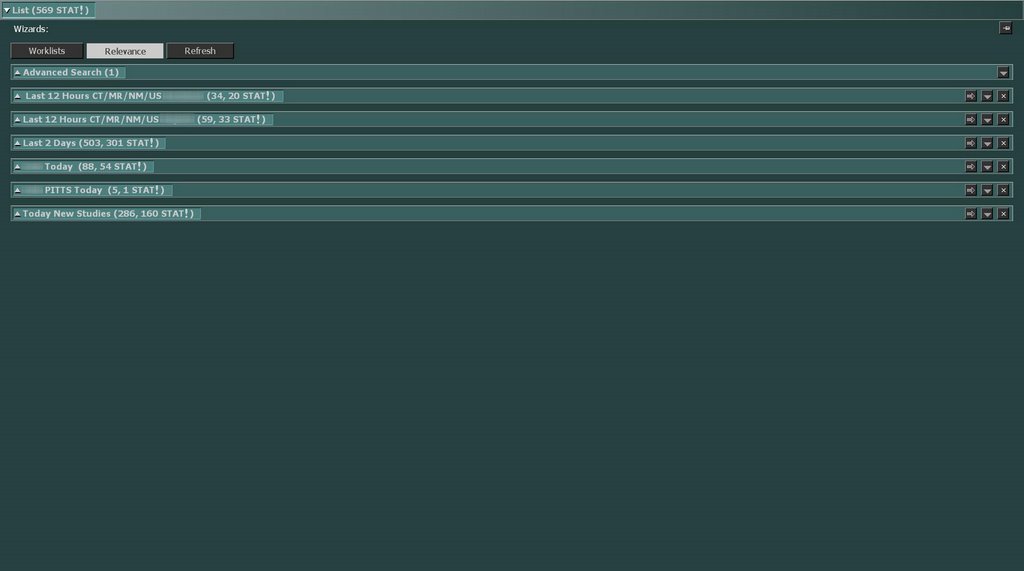
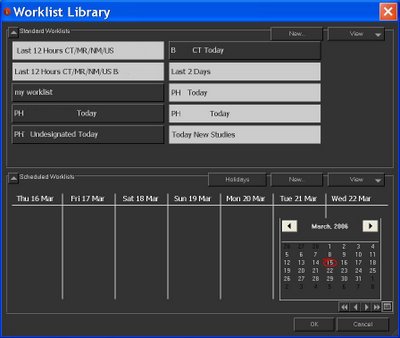
Once you're "in", you get this screen full of worklists. As I noted in the last post, the worklists are extremely customizable, down to the day and even the hour if you so choose. Everything I posted about the "Relevance" and the "Refresh" buttons is accurate, so I won't repeat anything.


I had noted previously that you can do Boolean-style searches, and the criteria for such a search are nearly unlimited:

There is a way to make your own worklist and even deploy it on some days but not others:

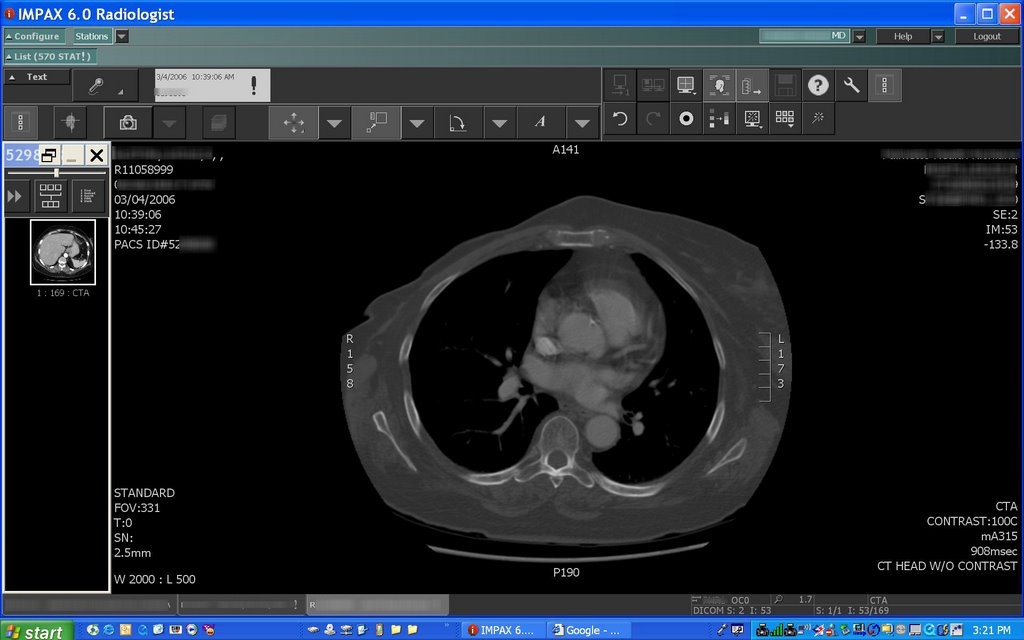
My ideal schedule would probably be no activity on any given day, but that doesn't pay the bills, does it? Anyway, opening a worklist gets you a list of patients and exams, and clicking one sends you to the actual viewer:

Ah, but wait! If you have only one screen, you toggle back and forth between the viewer and the data screen with the "Text" button. In fact, a lot of Impax 6.0 activity is based on toggling back and forth between screens in this manner. If you have more than one monitor, however, the images go off to the side, and you toggle between data and worklists, a more satisfactory experience. As I have posted earlier, the data or text screen has lots of very useful stuff like lists of priors, reports, and comment fields in which you can type your love notes to the ER. The panes can be easily resized and the program remembers what you did for next time.

I said before that the viewer is VERY similar to that within Impax 5.2 once you get past the slick reskinning, and I stand by that. There is still the necessity to use clone windows instead of dragging a sequence where you want to as many times as you want to. There is no "simple" MPR, and our web-deployed version doesn't have Voxar as yet. (I don't know if we will ever get that at home...) I have yet to dabble with hanging protocols, but the tool looks promising, at least. The button configuration scheme works just about identically to the old one:


This is too much configuration, in my humble, lazy, and somewhat Luddite-based opinion. I still prefer a more simple, streamlined approach. But that's just me.


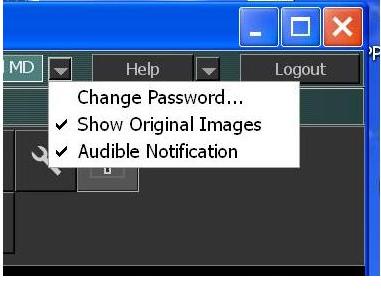
Now, here's a little peculiarity...to determine if you receive images compressed or uncompressed, you go to the upper right hand corner, click the triangle by your name, and check or uncheck "Show Original Images". This doesn't seem like a particularly logical place to put this, but then Saab puts the ignition switch on the center console. To each his own, just so long as I know where to look.

Forgive the necessarily brief overview, but what I am finding is that if you know Impax 4.5/5.2, you won't have much trouble with 6.0. That may be a good thing, but I do wish there had been a deeper overhaul. This product does get the Dalai stamp of usability, but mainly because I have spent a year with the older Impax's. But I do have to complement Agfa on what must have been a very difficult port over to .NET/CRL. This gave them the ability to deploy Impax 6.0 over the web, and that is a great achievement in and of itself.

I'll report more as the journey progresses.

Wednesday, March 01, 2006

9000 Visitors!

Visitor 9000 comes from Pasadena, California, via Verizon Internet. He (or she) was looking for information about using a Shuttlepro jog-dial with PACS. I've tried to do that, as you know, without much luck. For what it's worth, I got a keymap from a kind soul on the Agfa users' group. This will work for Agfa, and should work for other systems with minor modifications:

Button

1 ---F5
2 ---F6
3 ---F7
4 ---F8
5 ---page up
6 ---page down
7 -
8 ---page up
9 ---page down
10 -
11 --Enter
12 --F9
13 --Alt + Tab
14 --home
15 --end
---------------------------------------------------------------------------------------
jog left -----page up
jog right ---page down
---------------------------------------------------------------------------------------
shuttle in

Left 7 ---page up 60 frames/sec
Left 6 ---page up 45 frames/sec
Left 5 ---page up 30 frames/sec
Left 4 ---page up 15 frames/sec
Left 3 ---page up 10 frames/sec
Left 2 ---page up 5 frames/sec
Left 1 ---page up 2 frames/sec
Centered -
Right 1 --page down 2 frames/sec
Right 2 --page down 5 frames/sec
Right 3 --page down 10 frames/sec
Right 4 --page down 15 frames/sec
Right 5 --page down 30 frames/sec
Right 6 --page down 45 frames/sec
Right 7 --page down 60 frames/sec
---------------------------------------------------------------------------------------
Shuttle in transition (all) -

The old joke about 2001: A Space Odyssey, is that "HAL" was wordplay on IBM, one letter off for each, right? Arthur C. Clarke (or was it Stanley Kubrick?) denied this, claiming that it stood for Heuristic ALgorithm. Whatever. Gary Lockwood was one of the stars of the movie, along with Keir Dullea.


It is a little known fact, at least to those who don't dabble in such trivia, that Mr. Lockwood starred in the second Star Trek pilot episode, "Where No Man Has Gone Before", along with Sally Kellerman:

Because of the Star Trek connection, Mr. Lockwood is a frequent convention guest. The photo with my son below was taken at the 2004 Star Trek Convention in Las Vegas. Photos with a straight face are more expensive, I guess, although I did buy a copy of the famous "pod photo" above signed by both Mr. Lockwood and Mr. Dullea.

This all gives me an idea for a new podcast. How about "2006: A PACS Oddity"? All of HAL's memory now fits on a 2 GB thumb-drive, and Dave kills him by pulling it out of its USB socket. I'm sorry, Dalai, I'm afraid I can't do that....

Saturday, February 25, 2006

Who Owns Your PACS?
...An Online Poll

I'm doing a little research and I need your help. Please submit your answer to the poll below, and have your friends, colleagues, enemies, acquaintances, and anyone else connected with PACS do the same. Many thanks for your help! Just click the link below and answer the simple question:

Poll: Who owns PACS at your institution?

Thursday, February 23, 2006

ITL, Again...

ITL yanked their system, and I thought we were done with them. But alas, they have returned, and the "new and improved" version has been installed. Here is the description from one of my partners:

The system is counter-intuitive, has no cross reference tool on spine MR, and wastes screen space. The imaging tools are difficult to use, and multiple functions require using the "center" mouse button, which actually is the wheel. This is fraught with peril. The cursor travels to the imaging screen by moving down (?!?) off of the menu screen. The hanging protocol must be reset for every study. It has slowed me down so far. The touch screen remains, positioned horizontally, and is completely useless and ignored. Its only purpose is to NOT allow you to move closer to the screen without accidentally touching it and opeing a "toolbox" or switching to the next study.

As I told multiple people at (the site) yesterday, Pacs systems have evolved so that they all are fairly similar in interface. The important term is "evolved," meaning that natural selection has emphasized those traits which are most useful and eliminated the ridiculous and counterproductive. Any system that attempts to dramatically alter the interface (as ITL does) between radiologist and study is attempting to reinvent the wheel. And, as again in the case of ITL, square wheels don't roll real good.


Some improvement. ITL just doesn't grasp how the vast majority of radiologists in the world do their job. I would say that this is a case of engineering/IT types forcing what they perceive to be a "better way" upon us, but how they can think this horrendous approach is "better" is beyond me as a former engineer myself. Some of my people have spent hours with their engineers trying to make them follow our workflow. You've heard the old saying about a camel being a horse designed by committee. Well, this piece of junk is a PACS system designed with total disregard to patients AND radiologists. I'd rather have a camel.

The manager of the imaging center begged me to OK the use of this dog because he's bleeding out cash to pay for film. I gave him a lot of grief, asking why he keeps pursuing this dead-end after all my exhortations. He claims that one of the rads who will use it over at the imaging center gave a provisional OK, and the rest "didn't care." I suspect the one fellow who "approved" did so mainly because eliminating the touch screen meant that he didn't have to keep moving his head up and down, a real problem for him since he just had cervical spine surgery. This was taken as tacit approval from the entire group. As an aside, this points out how important personal communication can be, both within and external to your group. One of my guys gave a vaguely positive grunt, and so that is interpreted as being a huge vote of confidence by the entire group. Great.

I have told my people to use it ONLY if it improves their ability to read studies, and does not prove a hinderance. My personal feeling is to make the center choke on this purchase, give the history, but I'll try not to be too vindictive. We shall see how it goes.

Monday, February 20, 2006

Happy 1st Birthday, DoctorDalai.com!!


Neither the cake nor the child are mine, but you get the idea...

To be accurate, the first post went up on 1/29/2005, but I didn't start logging visitors until 2/18/2005, so that is the date I'll use for the "anniversary".

How far we've come in a year. I'm still tussling with Fuji, Agfa, and GE, still trying to get Amicas accepted at more places, and trying to get them to add a few important items, and I'm still at odds with most of the IT departments I work with (or work for as they seem to see it.) I did manage to get rid of ScImage in the past month, and we did get a "guru" on board at last.

Look for more interesting and weird developments in Year 2!

Tuesday, February 14, 2006

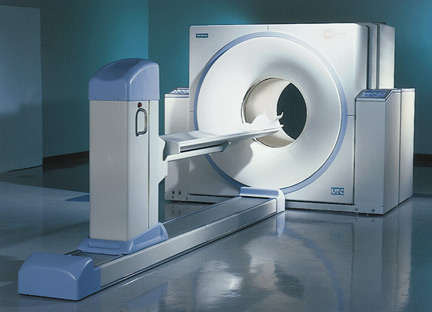
PET/CT Comes to Dalai's Hospital!
A Press Release

Dalai's Hospital adds Pet/CT scanner to its Diagnostic Arsenal
Unit is the first one of its kind in the state

Doctor Dalai's Hospital continues its leadership in imaging by adding dedicated PET/CT to its arsenal of diagnostic tools. Dalai's Hospital was the first hospital in the state to introduce positron imaging, initially with coincidence scanning in 1998. Dedicated PET imaging was launched in March 2001 and we now offers the state’s first fixed-site PET/CT. The new scanner combines PET and CT scanner technology to increase diagnostic confidence and improve patient management with faster scan times and higher-quality images.

“At Dalai's Hospital, we are always looking for ways to improve patient outcomes,” said the Hospital's Chief Operating Officer. “We’re glad to continue to lead in this diagnostic area by providing another much needed tool which gives physicians more detailed information to help patients. For us, its part of providing the quality healthcare to our community that Dalai's Hospital is known for.”

Positron Emission Tomography (PET) works by creating images of the biological functions of the body to reveal disease states. Prior to the exam, the patient receives an injection of a tiny amount of radioactive tracer, which emit signals as they travel through the body. Most scans utilize a positron-emitting form of glucose, which allows mapping of metabolism. PET measures the degree of sugar uptake, taking advantage of the fact that cancers use more glucose than normal tissues. The Computed Tomography (CT) aspect of the scanner improves the quality of the PET scan and adds an anatomical basis for localizing where the sugar or glucose uptake has occurred

This new class of PET/CT scanner, Siemens Biograph 16, is the first to utilize the proprietary lutetium oxyortho-silicate (LSO) crystals plus true 3D acquisition to allow faster acquisitions of images while improving image quality. No other manufacturer offers this critical technology. For patients, this means more comfort and confidence in the treatment of their cancer and other disease states.

Physicians believe that the improved images produced by the PET/CT could reduce the number of invasive procedures required during follow-up care, including biopsies and even unnecessary operations. “The quality of the images, and the added anatomic dimension, gives us greater ability to find and monitor disease,” said Dr. Dalai, radiologist and director of nuclear medicine at Dalai's Hospital.

Dr. Dalai added, “In fact, images produced by the new scanners are so precise that in some cases we have found malignancy that probably would not have been detected with any other technique. The addition of CT to the PET scan also helps us differentiate normal from abnormal tissues to a much greater degree than we could before.” Dr. Dalai is confident that the new combined PET/CT scanners will play a key role in continuing to improve patient care.

In oncology, PET/CT provides for early diagnosis, more accurate tumor detection and precise localization, improved biopsy sampling, and better assessment of patient responses to chemotherapy and radiation therapy. PET/CT also is used by cardiologists to detect certain types of heart disease and by neurologists for assessing disorders such as Alzheimer’s disease.

Sunday, February 12, 2006

"I'll Sleep When I'm Dead"


No, I've never heard of this movie either, but I think it did well in its native UK. Still the title is rather catchy, if disturbing, and introduces today's topic: Call vs. Sleep.

I've written a piece about overuse of imaging in the ERs and another one about night call. Nothing much has changed in the meantime. We do now staff the other hospital I mentioned, and there is a call service in place over there that does a very nice job from 11PM until 7AM. We have voted to extend the service's coverage to our entire practice, and this should be in place in a month or two, depending upon how quickly credentialing can be accomplished.

The whole concept of call troubles me, and it always has. Yes, I realize that people get sick in the middle of the night and require immediate care. No question there. However, the American public has been conditioned to come to the ER with any and every twinge, and once there, the ER has to X-ray, scan, or otherwise bless them with modern medical technology before they leave. There is a significant subset of ER patients known as "frequent flyers" whose charts are longer than the Encyclopedia Brittanica and whose Xray jackets from the old days of film have enough silver in them to make a car. (Of course now in the digital era they could get their jackets as their own personal Greatest Hits CD collection...a 15 disk K-Tel special.) I have taken to mentioning this in reports..."Today's CT of the head for altered mental status is compared to the 20 previous head CT's for the same indication, with the most recent prior study being from...." Bet I get in trouble for that eventually, huh? I have to confess with some degree of shame that I actually begin to get angry about reading these studies, and the more fatigued I get, the nastier I feel about it. A colleague tried to set me straight, if you will, by explaining the ER's attitude: "We do such a great job of diagnosis with a CT that they now rely on us completely." I'm supposed to feel better about that? Do you mean to tell me that medicine has become little more than imaging? No more Marcus Welby, M.D.? Pretty soon, we will be little more than auto mechanics (no offense, but you know what I mean.)

Anyway, a spot-check of ER clients reveals a potpourri of reasons for their selection of 3AM:

  1. The headache I had for the last 3 days got a little worse tonight.
  2. I work during the day.
  3. The ER isn't as busy at 3AM.
  4. The nurse at my Nursing Home just noticed this.
  5. I'm going on a trip in the morning.
  6. I'm scared.
  7. I can't afford a doctor of my own, so I came to the ER.

And so on. Frankly, I think this whole situation is an embarassing indictment of American Medicine. We have failed these people during the day, and so they come back to haunt us at night. I wish I had the answer to fix it. You can bet that if a certain female Senator from New York ever gets back to the White House, she will fix it, and us, with socialized medicine.

But back to the question of call and sleep. I chose the movie title as an opener to reflect the apparent views of lots of doctors in general, and radiologists in particular. Sleep? What's that? Only weenies need sleep. My talents are needed NOW. I'll sleep some other time. Basically, we can't or won't realize that we (and our colleagues) have to sleep. But pushing ones' self to the limit and continuing to work after 24 or more hours of wakefullness is a really bad idea. I can cite article after article after article that shows we make more mistakes when sleep-deprived. It's a no brainer (almost literally!) Somehow, in Medicine, we don't take this for granted as we would in any other industry or situation. DM Gaba noted in a paper presented at the Proceedings of Enhanced Patient Safety and Reducing Errors in Health Care in 1998 that,

...in most high-hazard industries the assumption is that fatigue and long, aberrant work hours lead to poor performance, and the burden of proof is in the hands of those who believe that such work practices are safe. In medicine, concerns over discontinuity of care, and difficulties in changing medical culture have pushed the burden of proof into the hands of those who wish to change the status quo. Given that medical personnel, like all human beings, probably function suboptimally when fatigued, efforts to reduce fatigue and sleepiness should be undertaken, and the burden of proof should be in the hands of the advocates of the current system to demonstrate that it is safe.

The sleep-deprivation starts in medical-school, and was long institutionalized by internship and residency. In the past few years, government regulation has limited resident's weekly hours to 80, and their continuous shift time to 24 hours. This presents somewhat of a problem in staffing, and there is indeed an impact upon the continuity of care by the residents. Still, does the benefit of continuity override the detriment of an exhausted resident pushing the wrong drug, or falling asleep whilst operating? These things have indeed happened, you know. (Or do you?)

My interest and maybe ire were rekindled by an presentation from Nabile Safday, M.D., cited in RSNA News. Dr. Safday found lots of interesting stuff, like radiologists have good vision by and large with mean acuity of 20/16, better than normal. But here is the part that hurts (italics are mine):

When asked, “Have you ever fallen asleep while driving after being on-call overnight,” 28.5 percent said, “Yes.” Almost half (47.6 percent) said they had nodded off while reading a patient study during on-call hours. Finally, the trainees self-reported that an average of 17.5 percent of errors they made on-call were due to a lack of sleep.

Bottom line: we are hurting EVERYBODY involved by pushing ourselves to the limit in this manner. We are guaranteed to make more mistakes in reading, and anyone who says they are as accurate after being up all night is fooling you, and probably him/herself. I couldn't find any figures on whether any rads or other physicians have actually died in car crashes attributable to sleep-deprivation, but you can bet it has happened.

So why do we do this to ourselves? About 95% of the answer is MONEY. Covering your hospitals, and especially your ER's, is a zero-sum game. Either you do it yourself, you hire more people to do it so you all have call less often, you hire a nighthawk to do it for you, or you hire a call service to give prelims (or final reads). The only currency we have is money and time off. If my partners and I take call and then work into the next day, as we are doing now, we get more money (ignoring for the moment the fact that a lot of ER cases don't pay anything), and we allow somebody else to be off the next day. Our theory has been that you can't enjoy the day off after call anyway, because you are so tired, so you might as well work a half day, right? Wrong, buffalo-breath, but not everyone agrees with me. If you don't want to pay a call service, and you don't want to hire an internal night-hawk, there is, of course, the option of going to shift work. Some of my partners think this is a great idea. One would work a week of 11PM to 7AM, with the day off afterwards. Just wonderful. Except there is one problem...remember the zero-sum calculation. Somebody has to be working during the day for the call guy to be off! So you see, this is yet another form of robbing Peter to pay Paul. You can't get something for nothing, you know.

Personally, I think the internal 'hawk is the way to go, but those birds are few and far between, and they don't seem too disposed to coming to our little town. There isn't much to do here during the day, so why come here to work at night? That leaves the call service, and this is the path we have decided to follow. There are those who are not happy about the cost of $50 per study, and that for just a preliminary report that we will have to reread in the morning. But tell me, what price do we put on our patients' health? Or our own, for that matter? Hmmmmm?

Wednesday, February 08, 2006

The CR Ballad

Come 'n listen to my story 'bout my new CR.
It cost a pretty penny but the pitchers sure were poor.
But then one day we were lookin' at a chest,
And darn if it weren't lots worse than all the rest...
Missed a Pneumo...got in trouble...
Well, the first thing we did was to call the service boys,
And they all said, "ain't a problem with our toys,
Any product with our label is as perfect as can be,
It's gotta be yore doggone PACS that will not let you see..."
DICOM problems, or somethin'
So we called up our PACS service boys, and this is what they said:
"We don't mess with any data or with any DICOM head.
What the CR sends to us is what we send on to your station,
The FDA don't let us alter yore interpretation"
So they got out every service guy from east of Tennessee,
And they worked on it for hours just for you and just for me.
And doggone if they didn't make it better than before,
So I don't have to kick that darn machine right out the door.
Gonna keep it, since it works now.
Here's the moral of the story, folks. On this you can depend:
A lot of finger-pointing gets you nowhere in the end.
If yore CR's lookin' crummy and you can't DICOM-Retrieve,
It could be that your current vendor really ought to leave.
Or at least help you out, like ours did. Y'all come back now, hear?

Monday, February 06, 2006

The Caveman Ad

No, it has nothing to do with PACS, but this was by far my favorite Superbowl XL ad...

Sunday, February 05, 2006

DoctorDalai.com joins Hitsphere!

This weblog has just been accepted into the HITSphere! It isn't an easy task:

The HITSphere is a network of premium weblogs that write content about the healthcare, medical, and clinical informatics and information technology (IT) industry. Combined, these sites reach a large readership of influential healthcare technology professionals. Learn more.

Many thanks! Be sure to check out the other (much more) illustrious blogs.

Saturday, February 04, 2006

Adult Image Detection


Images courtesy of ContentPurity.com


Every so often, I succumb to the urge to click an ad on a Google search. This morning, I decided to "scan my computer for unwanted porn". I guess there must be some way to tell the difference between "wanted" and "unwanted" porn. I ran the scan, and about all it found were articles and references to mammography stored on my computer. Wow. (Those were "wanted", by the way.) I wonder if it will report you if you have nekkid baby pictures of your kids on your computer.

The website itself had this interesting note on their technology, called Adult Image Detection: "An advanced algorithm is used to detect adult images by assessing skin-tone levels and distribution." The image above gives you the idea, although I'm not sure the young lady's epidermis was detected by this algorithm, or just with something like Photoshop's magic wand tool for the example.

The process might lend itself to the radiological world. I know there is a lot of work being done in CAD (Computer Aided Diagnosis) and such. I use one form of this for mammography, but honestly, the machine misses more than it finds, and flags stuff that isn't there. Maybe something simple like looking for contiguous bands of density (like a subdural bleed) would be a start.

Just a thought. You never know where you might find ideas for new approaches to things.

Thursday, February 02, 2006

8000 Visitors!


Visitor 8000 comes here via Cox Communications in San Diego, California. Isn't it amazing that yet another thousand folks came here to look around with very little new content? I'm actually rather ashamed of the slow progress, but that will change. We are in the process of building my own personal PACS (OK, my group is paying for it, but I still like to think of it as mine.) Stay tuned for all the gory details...

Tuesday, January 24, 2006

New PACS Workstation Design


I know I've been disappointing my readers with my lack of blog activity. My group has taken on a new hospital, and the hours are rather long, giving me less time to indulge my fantasies of being a writer. I was on call at the new place this past Saturday, and I did not leave my seat from 8AM until 2PM. Therefore, I propose the above modification for PACS stations at that hospital. It shouldn't be too expensive, as long as we don't contract with the Air Force for the seat components...

How to make a RIS-less RIS


There aren't too many pictures that come up when you search for "RIS", so how about a flourless chocolate cake instead? RIS-less, flourless, what's the difference?

This post may disturb my friend Mark, who recently left Amicas for Empiric Systems, the creators of a very nice web-based Radiology Information System, or RIS. I am going to tell you how I'm going to forgo purchasing his product for my independent PACS operation, and that means he won't be selling me one for a while. It's a great system, but I need to trim my costs where possible.

Speaking of Marks...some of you may know I tried to hire back a PACS guru named Mark M., who was driven out of town for various reasons by a certain IT empire. Fortunately for him, but unfortunately for me, he likes his new spot, and he couldn't be lured back to my place. But Fate always has something interesting up her sleeve. Our PA came to me one day and said, "I know this really great PACS guy, who might be interesting in your weird, I mean progressive ideas. He is thinking about moving, so why don't we get in touch with him?" What's his name? Mark S! Must be karma again. He came to look around, liked what he saw, and we now have our PACS guru. He is already hard at work creating our independent system, and I'll report back as we progress.

Anyway, back to RIS's or the lack thereof. To achieve the RIS-less RIS, you must first define what you need out of such a contraption. At the bare minimum, we need to attach demographics and reports to a study. Yes, a RIS can provide much more than that, but keep in mind, the clients for our little operation are mainly clinicians with scanners in their offices (DON'T even say it...), with relatively small volumes and internal billing and scheduling. Therefore, we can stick to the very basics, at least for now.

I have mentioned PACSGEAR in earlier posts, and I had the chance to meet some of their staff and play with their products at RSNA. They offer two products that solve my "RISsy"-fit, and later I'll tell you about a third that is really nice.

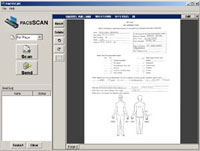
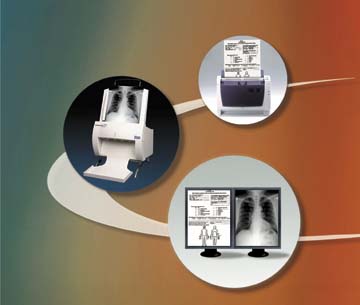
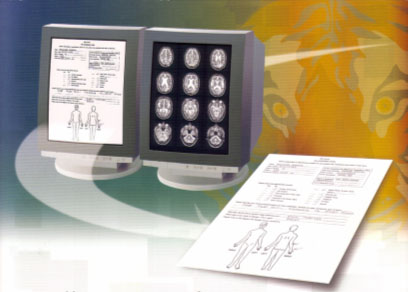
This illustrates the concept: You have a sheet of demographics, history, or whatever that you want the rad to have available with the scan. With the PACSGEAR PacsSCAN program, you just scan the piece of paper with a regular old TWAIN document scanner (they recommend a heavy-duty version rather than the $25 Best-Buy bargain), bring up

the patient in question via the little dialogue window ("Lookup" will fetch the pertinent info from your PACS or RIS if you have one), and off you go. Just press SCAN and the document becomes yet another DICOM sequence in the designated exam. Couldn't be easier.

Print2PACS does something similar, but instead of scanning a physical document, you quite literally print a DICOM image into your examination. With this little program, our transcriptionists can print the report straight into the system, where it can be viewed along with the rest of the examination. Print2PACS makes it possible to store other things like DEXA or cath reports, or even JPEG images if you have a need to do so. Now, this isn't a perfect solution. What you get on the viewing end is a picture of a report, and it can't be edited or minipulated. (I suppose you could play with its window and level, and magnify it if you wanted, but you can't change any of the words.) Still, it gets the report in front of the clinician, which is the goal.

The third product in the PACSGEAR suite is one that doesn't really contribute to the RIS idea, but it is great for our purposes none the less. PacsSCAN Film adds a film digitizer to the picture, if you will, and will scan yucchy old film into your shiny new PACS system. But it goes one step beyond just digitizing...it will divide out sheets of multiple images into understandable sequences that fit right in on the PACS workstation. No more big picture full of smaller images that you have to pan around to view. This is a great thing for those of us reading from sites who are still filming.

I have to add that there are free programs out there that do much of what we're talking about here, basically converting .TIFF or conventional print files to DICOM. I've played with some of them, and while they do actually work rather well (especially for being free), they are not as smooth and elegant as the PACSGEAR products. Therefore, PACSGEAR gets the Dalai Seal of Usability. I'm looking forward to being one of their customers.

Sunday, January 15, 2006

A Quote from "The Ascent of Man"

Let me take a moment to introduce you to a life-changing passage. Some of you may recall the PBS series, "The Ascent of Man", a series of essays brought to life by the philosopher Dr. Jacob Bronowski. We in the health-care field aspire to the designation of "scientist", and to the acquisition of knowledge. We must keep in mind, however, that knowledge has to be tempered by humanity. The passage which I have quoted below, is, in my opinion, one of the most poignant and important things I have ever encountered:

THERE ARE TWO PARTS to the human dilemma. One is the belief that the end justifies the means. That push-button philosophy, that deliberate deafness to suffering, has become the monster in the war machine. The other is the betrayal of the human spirit: the assertion of dogma that closes the mind, and turns a nation, a civilisation, into a regiment of ghosts — obedient ghosts, or tortured ghosts.

It is said that science will dehumanise people and turn them into numbers. That is false, tragically false. Look for yourself. This is the concentration camp and crematorium at Auschwitz. This is where people were turned into numbers. Into this pond were flushed the ashes of some four million people. And that was not done by gas. It was done by arrogance. It was done by dogma. It was done by ignorance. When people believe that they have absolute knowledge, with no test in reality, this is how they behave. This is what men do when they aspire to the knowledge of gods.

Science is a very human form of knowledge. We are always at the brink of the known, we always feel forward for what is to be hoped. Every judgment in science stands on the edge of error, and is personal. Science is a tribute to what we can know although we are fallible. In the end the words were said by Oliver Cromwell: 'I beseech you, in the bowels of Christ, think it possible you may be mistaken.'

I owe it as a scientist to my friend Leo Szilard, I owe it as a human being to the many members of my family who died at Auschwitz, to stand here by the pond as a survivor and a witness. We have to cure ourselves of the itch for absolute knowledge and power. We have to close the distance between the push-button order and the human act. We have to touch people.


Jacob Bronowski
The Ascent of Man
BBC, 1973

Monday, January 09, 2006

PACS WARS
...Coming to a Hospital Near You


With apologies to George Lucas, and anyone else who ever had anything to do with Star Wars, including those who watched the movie, not to mention PACS and IT personel around the world...


In a Radiology Department in a Hospital far, far away….

PACS WARS

Radiologist NEMA Organic, sends a desperate message for help…..before being taken prisoner by the evil IT Empire aboard its Death SAN…..
Young PACS administrator Luke DICOMmer hears her plea, and together with PACS guru OhbigWAN Pirogue, mounts a frantic search across the enterprise.

They enlist independent service guys LAN SCSI and his sidekick TapeBackup, whom they find at the LossyCompression Canteen. Along with their faithful laptops, QR and ICUP, they take off in the Millenium RadNet to save their helpless heroine.

Watch as they battle DarthRAIDer and the CIO of the IT Empire aboard the Death SAN. Witness the climactic laser pointer battle of good against evil. See studies broken and patients merged. Watch as the fate of the enterprise hangs in the balance!

PACS WARS.
Coming to your hospital.


May this farce outwit you.

Wednesday, January 04, 2006

Seven Thousand Hits!


Wow. Congratulations to the 7000th visitor, from Source Medical in Birmingham, Alabama.

It seems like just yesterday we were at 6000. Actually, it was about three weeks ago. Time flies when you're having fun. The first anniversary of Dalai's PACS Blog is coming up pretty soon. I'll have to come up with something appropriate.....

Monday, January 02, 2006

DICOM Your CD-ROM!
Another AuntMinnie Thread


Periodically, the issue of why Amicas (and Stentor, oops, I mean Philips, iSite) don't burn DICOM CD-ROMS comes up on AuntMinnie.com. The fact is that neither PACS system does this, at least for now. I do believe Amicas will be adding this functionality shortly. In the meantime, there are a few options:
  1. Buy an eFilm License from Merge (if you didn't get one as a QC station originally), at a cost of $950 per year or $3100 for an unlimited time license.
  2. Use the FREE product from K-PACS that does more or less the same thing, and includes a viewer.
  3. It is actually possible to open a study from within Amicas LightBeam and then save it and manually burn it, but this has too many chances for error.

The thread got rather contentious, which seems to happen a lot on AuntMinnie. Even David Clunie weighed in on this; apparently he receives a very large number of non-DICOM disks from Amicas sites and it makes his life miserable. Dr. RW cited a case of something missed because someone had to compare a non-DICOM study on one machine to the DICOM study on their PACS workstation. (This is exactly why I think the Napster PACS idea has come of age.) Mr. Clunie actually advocated avoiding Amicas and others that don't burn DICOM CD-ROMs.

Given the other methods that exist to get the DICOM CD-ROM, I think it is a little drastic to tell people to avoid a PACS system on that criterion alone. Remember, never buy a PACS based on one particular bell or whistle (even a very important one), or you'll end up with a ScImage or ITL type product. Avoiding a system on the same basis will exclude some good companies. Still, I DO think Amicas and Philips need to get their DICOM-burning software finished yesterday.

For those CD's already out there, I wonder if there is a translation program that will convert an examination from Amicas or iSite (or for that matter Siemens proprietary ECAT PET) to regular ol' DICOM format? I know a few people that would gladly pay a reasonable amount for something like that. I have found a few pieces of software over the years that will do the conversion to some degree, although the process is rather painful and not worth it in the end. Once someone creates this, they may feel free to pay me a 10% royalty for the idea.

News Flash!!!

Andreas Knopke just posted this on the AM thread:

Hi Dalai,

We already contacted Stentor in order to get some information on their proprietory image format but without any luck. They answered with something like "DICOM will be supported soon". Amicas' JPEG2000 + XML template format will be supported soon by our DICOMReader ( free download at http://www.dicomreader.com) because it is quite easy to "dicomize" it.

Regards, Andreas

Thanks, Andreas! Great minds think alike, huh? Don't worry about my royalty, just make sure everyone knows about this!

An AuntMinnie Thread about Siemens Syngo PACS


Sometimes, discussion threads on AuntMinnie.com become a little contentious. Take in point this thread about Siemens Syngo PACS. I won't copy it here, but suffice it to say that a question about this product morphed into a rather long discussion with an entrepreneur by the name of Stephen Levkoff, PhD.

Dr. Levkoff started out in the financial world, and amassed a great deal of expertise in computers and databases. His fame was tarnished somewhat by a famous failure, Decision 2000, which he created for Reuters. The Observer notes:

But Reuters' attempts to compete with Bloomberg led to financial disaster and a series of lawsuits. In 1989 the company hired a former Smith Barney executive, Stephen Levkoff, to devise a bonds analysis database to rival Bloomberg. But the product, released as Decision 2000, was regarded as a technological disaster and cost $10m after Levkoff sued.
Another lawsuit, from brokerage house Cantor Fitzgerald, followed over a failed joint venture through which Cantors would provide Reuters with a live feed of US Treasury securities prices.
Even worse was to follow with Reuters' next project, codenamed 'Armstrong', an ambitious attempt to correct what it had failed to achieve with Decision 2000 - fusing real-time market data with legacy information. Armstrong proved to be another huge disaster and cost the company some $20m.


In the interest of fair and balanced reporting, Dr. Levkoff responded thusly when I posted this snippet:

In response, I saw the Observer many years ago. It was an attempt to hammer Reuters for its incompetence in financial markets other than foreign exchange. Reuters failed in two major deals with two industry experts: Cantor Fitzgerald (government bonds) and me (multicurrency analytic systems). In my case, they wanted to integrate D2000 functionality into ALL Reuter terminals –but with no royalty payments. The business landscape is littered with numerous other IP vendor lawsuits against Reuters for various material breaches of contracts, bad, faith and lack of fair dealing. Cantor Fitz and I had the wherewithal, strong legal position and balls to fight back. We won – more than you will make in a lifetime as a radiologist in private practice.
I didn't respond to the Observer nor will I now. I consider the Observer article libelous – incorrect and uninformed. D2000 was extremely successful. Clients in 30 countries were serviced by 6 redundant data centers via a failsafe global network. It significantly undercut the "Reuters Terminal (RT)" - a proprietary PC platform that delivered nothing but real time data that was only a small part of D2000.
Decision 2000, a highly viable multi-lingual Bloomberg competitor with operations in 30 countries, subsumed the RT functionality and offered more advanced real-time analytics than Bloomberg has today - in an industrial strength platform. D 2000 became a $250 million disaster for Reuters AFTER I sold it to them - they mistakenly did not understand the financial markets or the expertise necessary to compete. They hired 1000+ (semi-competent) people to attempt to do what I had done with 150. They bombed badly and attempted to blame me long after I left the company. If you can read, you should review the federal case that we brought against and books written by insiders at Reuters. D2000 comes out very well.

Dr. Levkoff's goal is to "develop and acquires very high end multi-modality imaging centers." What differentiates him from a hundred other similar operations is that he wishes to apply his years of expertise to the world of health-care informatics, PACS, RIS, and so forth. His analysis

"...found that Siemens Syngo Suite offers the only fully integrated, industrial strength RIS/PACS solution in the market. The platform - Fujistu Siemens servers, Sun Solaris (UNIX), Oracle (db), EMC (storage) - is the only one in the industry capable of supporting multiple, fully redundant data centers with real-time database replication and synchronization. At the June 2005 SCAR meeting in Orlando, most vendors not only completely failed our platform requirements but scoffed at our requirements for a completely fail-safe, multi-data center integrated health care information environment. However, post-Katrina, the need should be obvious to all health care executives."


Interesting analysis, but when I posted this, Dr. Levkoff decompensated:


If bullet-proof, uncrashable hardware was the end-all to end-all, we would all still be using UNIX on Sun boxes. Somehow, Katrina or no, that has not been first and foremost in everyone's mind. Wintel boxes are considerably less expensive, and with off-site storage, you should be covered. The best Unix box hooked up to the best SAN becomes inoperative when immersed in water, last time I checked.
The Siemens Syngo/eSoft approach is very esoteric (read: strange) although it does work well once you get used to it. They have unified the appearance of their modality controls and workstations, and from a very brief peek at RSNA, their PACS uses the very same interface. That is a good thing to some extent, but how many rads are going back into the control room and running the CT scanner? I personally don't think this interface is the easiest or the most straight forward for PACS use. It has certainly been a long time in coming. I would be curious to hear from any rad who is using this product.


His response:

Hello Dalai Lama - You sound like a weak Siemens competitor. Your Wintel comments are extraordinarily naive - typical of the industry. Microsoft does not offer an industrial strength operating system for zero-downtime environments - particularly across data centers. Further, you obviously don't understand the concept of running multiple, fully redundant data centers with real time database replication....On the user interface issue, you may find it "strange" because you are accustomed to doing things a certain way. Loosen up - it’s very intuitive and flexible. Additionally, commonality of user interface across applications and modality is essential for training, cross-training, quality control, and leveraging personnel for operating efficiency. As a CEO, I would not make a purchase decision that did not offer all of the characteristics of the Siemens Syngo Suite, given its availability. Also, I wouldn’t hire a radiologist who couldn’t scan.


Just a little bit over the top. I won't keep quoting the thread, but suffice it to say that things went straight downhill. He became more and more angry and condescending with every post. I finally gave up and invoked the "Dalai Shroud", declaring Dr. Levkoff deceased with respect to my future interaction with him.

Daniel Braga, another AuntMinnie poster, has the last word so far on the thread, asking the most pertinent questions of all:

How many radiologists did you meet with to discuss their impressions of the viewer? How many hospitals did you visit using the product that you would be buying?
Dr. Levkoff is obviously a very brilliant man, and has done a great deal research in PACS and healthcare informatics. Unfortunately, his wisdom has manifested itself into tunnel vision, and he has sandbaged himself into a particular corner. Even more sadly, he cannot tolerate the disagreement over his choice of, well, corners, and he has lashed out to the point of destroying his credibility, at least to me. He had much to contribute, but in trying to change the entire industry in one fell swoop, he lost his chance to do so meaningfully. RIP.

Predictions for 2020 by Digital Doctor

Digital Doctor has posted several incredibly eloquent messages on AuntMinnie.com. Here are his predictions for 2020, which I suspect will turn out to be right on target:


The Future of Medical Imaging - 2020’
By: Digital Doctor
Sat 31 Dec 2005


My Predictions for 2020!


Government Regulations
In the United States, we will face a healthcare CRISIS on or before 2017 due to a lack of funding for Medicare and Medicaid. As Medicare and Medicaid are the "insurers" for approximately 30% of all medical care in the United States, you can perhaps only imagine the potential for havoc. The United States CARE Act will be passed prior to 2012, which will mandate federal registration of radiologic technologists. PACS Systems Analyst (a radiographer with minimal certification in PACS), PACS Administrator and PACS Manager will become recognized growth opportunities for radiographers. Registration will be required as part of the CARE Act. Many clinicians will truly question the necessity of radiologists (but not for the first time) and a political struggle will ensue for the future of medical imaging. Ultimately, radiologists will win for several reasons despite the overwhelming anti-radiologist movement. Radiologists will put more weight behind the radiographer role as well so that the two professions will be inseparable to better support their own role.


Expansion of Services
Medical Imaging will, of course, become an even more integral component of healthcare as (in the United States) utilization will continue the trend of expansion of 7% every year. Medical Imaging will assume as much as 25% of total hospital revenue on average.


Expansion of Roles
The Radiology Practitioner (introduced in 2003) will become an essential role in the United States due to expanded utilization of services and a reduction in reimbursement. Physician Assistants have been assigned to Radiology Departments since least 1995, which I would argue fulfills a similar role, as both the Radiology Practitioner and Physician Assistant are "physician extenders." The Radiology Practitioner will require a Masters Degree and two years residency (in addition to four years practice and registration in a Medical Imaging specialty).


Technology
The "One Touch" scan will revolutionize technologist workflow. Technologists will be able to focus attention on patient care and post-processing. OLED monitors (displays) will be the predominant technology of the day; however, OLED will soon be replaced by 3D Holographic displays which will offer the first "true" 3-Dimensional views of the human form in medical imaging.
"Personalized Medicine" (the most overused medical "buzz" phrase of the current decade) will finally be a reality at about the same time as healthcare in the United States nears collapse. Driving "Personalized Medicine" will be the introduction of several new "multi-modality" scanners. An “Omni Scanner” will be introduced that is able to perform diagnostic radiographs, Computed Tomography, as well as Magnetic Resonance and Nuclear Medicine scans.


TRIP (Transforming the Radiology Interpretation Process) by SCAR will become an extended initiative. By 2020 radiologists will interact visually, verbally and tactilely with PACS (renamed Medical Imaging Informatics in 2008). The radiologist will don gloves that will act as a virtual keyboard, a mouse and a multimedia controller (think the "Shuttle Pro" by Contour Design) "all-in-one." PACS systems will offer, "Visual memory cues" (not CAD) that will act as mnemonic prompts for radiologists and clinicians to remember specific patients and abnormalities. PACS will track and respond the eye movements so that visual fixations will result in image zoom and pan or will activaate functions upon which the user has a visual fixation.


AN ENTIRELY NEW MODALITY WILL BE INTRODUCED which will assume much of the workload of Computed Radiography and Digital Radiography. The new modality will not utilize ionizing radiation as a means for imaging. The new modality that will (possibly) continue to be known as Digital Radiography will undergo the most dramatic changes, as "unlimited" radiographers will utilize equipment that is more similar to Computed Tomography than Computed or Digital Radiography. Radiography Equipment will become much more portable so that the "Radiography Suite" (not the portable machines of today) will be portable. Computed and Digital Radiography will often acquire tomographic images from which 3D images will be automatically constructed by the modality. Computed Tomography will "top off" at 2048 "slices" which will become the new "unbreakable barrier" for years to come. Computed Tomography will automatically generate any required MPR, MIPS and even 3D volumetric series.
Nuclear Medicine and Magnetic Resonance (and likely Computed Tomography to some degree) will be the true driving force of the "Personalized Medicine" trend. Nuclear Medicine, in particular, will lose the moniker "Unclear Medicine" as images will begin to resemble the image quality captured in the 256 "slice" Computed Tomography images of 2008.
Computer Aided Detection will become so ubiquitous that CAD will be a standard feature on every modality. Every modality will utilize CAD for nearly every conceivable procedure that will increase in-office utilization of Cardiologists and nearly every medical specialty group.
Structured Reporting will become a reality and will drive major changes to the workflow of radiologists. In fact, Structured Reporting will be hailed as the "saving grace" of Radiologists. The innovations related to Structured Reporting and CAD will so alter the job function of radiologists that the profession of radiologist will either disappear (not likely) or become more interventional (especially as radiation therapy and nuclear medicine take on many new roles) or radiologists will offer "value added interpretation" (very likely).


Educational Trends
In response to the CARE Act and technological innovations the minimum educational requirement for radiologic technologists will be an Associates Degree (two years post primary school). More offerings of advanced degrees will be available for technologists seeking to specialize. Magnetic Resonance will have been recognized as a "primary modality" by the ARRT before 2012.


Even more COOL stuff on the horizon in 2020
BEYOND SIMPLE IMAGE DATA...Radiologists will utilize tactile and auditory senses by donning a suit that will provide additional sensory data to perform diagnosis - this data will be derived from image data (or data collected during the scan). Surgeons and Interventionalists will be able to utilize this data to perform remote surgeries. WAVELET COMPRESSION utilized by nearly every PACS and modality will be replaced very soon with "Fractal Compression" which will finally compensate for the overwhelming data sets generated.

Seen at the Westin Savannah


Forgive me, but I saw this vehicle and its, um, accessories, in the parking lot of the Westin Savannah, and I just had to share. If anyone is offended, I'll remove this post, but hey, it isn't my truck!

And while I'm at it, is this a case of X-Ray Vision?